The Invisible Pain of Breastfeeding
Breastfeeding is universally recommended for infant development, but the biomechanical reality of the nursing mother is frequently overlooked. Women who breastfeed spend 3 to 6 hours a day in cervical flexion and increased thoracic kyphosis — holding the baby in a fixed position, often without adequate arm support. This posture, repeated dozens of times a day over many months, produces a predictable cascade of musculoskeletal pain.
Pharmacological restriction compounds the problem: most analgesics and non-steroidal anti-inflammatory drugs (NSAIDs) — except acetaminophen and ibuprofen at limited doses — are contraindicated or used cautiously during lactation. Muscle relaxants are generally avoided. This creates a therapeutic gap that medical acupuncture can help to fill: a non-pharmacological intervention, with no transfer of substances into breast milk, and a favorable safety profile — adverse events are predominantly mild (local hematoma, vasovagal syncope, and rare cases of pneumothorax).
The Biomechanics of Breastfeeding and the Origin of Pain
Nursing posture imposes specific biomechanical demands on the entire posterior chain of the trunk and neck. Cervical flexion of 30–45 degrees to look at the baby, combined with shoulder protraction to support the infant, produces an overload pattern biomechanically and pathophysiologically identical to Janda's upper crossed syndrome — with the added burden of frequent repetition and sleep deprivation.
Biomechanical Pain Chain in Breastfeeding
Cervical flexion + shoulder protraction
Posture held for 30–60 minutes per feed, 8–12 times a day. Overloads the upper trapezius, levator scapulae, rhomboids, and thoracic paraspinal muscles.
Increased thoracic kyphosis and pectoral shortening
Repeated shoulder protraction shortens the pectorals and weakens the scapular retractors (rhomboids, middle trapezius). Increased thoracic kyphosis compresses the costovertebral joints.
Chain formation of trigger points
Trigger points form in the overloaded muscles: upper trapezius (cervical and temporal pain), rhomboids (interscapular pain), thoracic paraspinals (dorsolumbar pain), and pectoralis minor (anterior shoulder pain and breathing restriction).
Worsened by sleep deprivation and peripartum hypermobility
Chronic sleep deprivation lowers the pain threshold. Relaxin, a pregnancy hormone that affects ligament tone, may persist at residual levels in the immediate postpartum period — its direct role in postpartum myofascial pain is not yet fully characterized. Periarticular joint hypermobility appears to be a relevant factor: it forces muscles to work harder to stabilize joints, amplifying trigger point formation.
- Nursing posture imposes specific biomechanical demands on the entire posterior chain of the trunk and neck.
- Cervical flexion of 30–45 degrees to look at the baby, combined with shoulder protraction to support the infant, produces an overload pattern.
- That pattern has the added burden of frequent repetition and sleep deprivation.
Why Acupuncture Is Ideal for Lactating Mothers
Pharmacological safety during lactation is a legitimate concern for every mother. Opioid analgesics pass into breast milk and may cause infant sedation and respiratory depression. NSAIDs such as diclofenac and naproxen have limited safety data in lactation. Muscle relaxants (cyclobenzaprine, carisoprodol) fall into risk categories and are generally contraindicated.
Analgesic Options During Lactation: Comparative Safety
| Therapy | Lactation safety | Efficacy for myofascial pain | Notes |
|---|---|---|---|
| Acetaminophen | Safe (L1) | Limited for myofascial pain | Does not treat trigger points |
| Ibuprofen | Safe (L1) at standard doses | Moderate for the inflammatory component | Does not treat trigger points |
| Diclofenac | Probably safe (L2) | Moderate | Limited data in prolonged lactation |
| Muscle relaxants | Avoid — insufficient data (L3–L4) | Moderate | Risk of sedation in the infant |
| Medical acupuncture | Favorable safety profile — non-pharmacological intervention | May reduce myofascial pain in available studies | Targets myofascial trigger points |
Treatment Protocol for Lactating Mothers
The medical acupuncture protocol for lactating mothers is tailored to the particularities of this stage: shorter sessions (to fit breastfeeding schedules), comfortable positioning (side-lying or seated — avoid prone with engorged breasts), and attention to breast structures (avoid points on the breast and nipple).
Adapted Protocol for Lactating Mothers
Mapping the pain chain and postural guidance
We identify trigger points, evaluate nursing posture (with photo or video), and guide infant positioning, nursing pillow use, and arm support.
Needling of priority trigger points
Dry needling of the upper trapezius, rhomboids, and thoracic paraspinals. Sessions of 20–25 min, side-lying or seated. The mother can breastfeed immediately afterward. 2 sessions per week.
Systemic electroacupuncture and residual trigger points
We add electroacupuncture at GB21, SI11, BL17 for thoracic segmental modulation, and treat residual trigger points in the pectoralis minor and scalenes. 1 session per week.
Biweekly sessions until weaning
Biweekly maintenance throughout breastfeeding. Periodic postural reassessment — posture changes as the baby grows and gains weight.
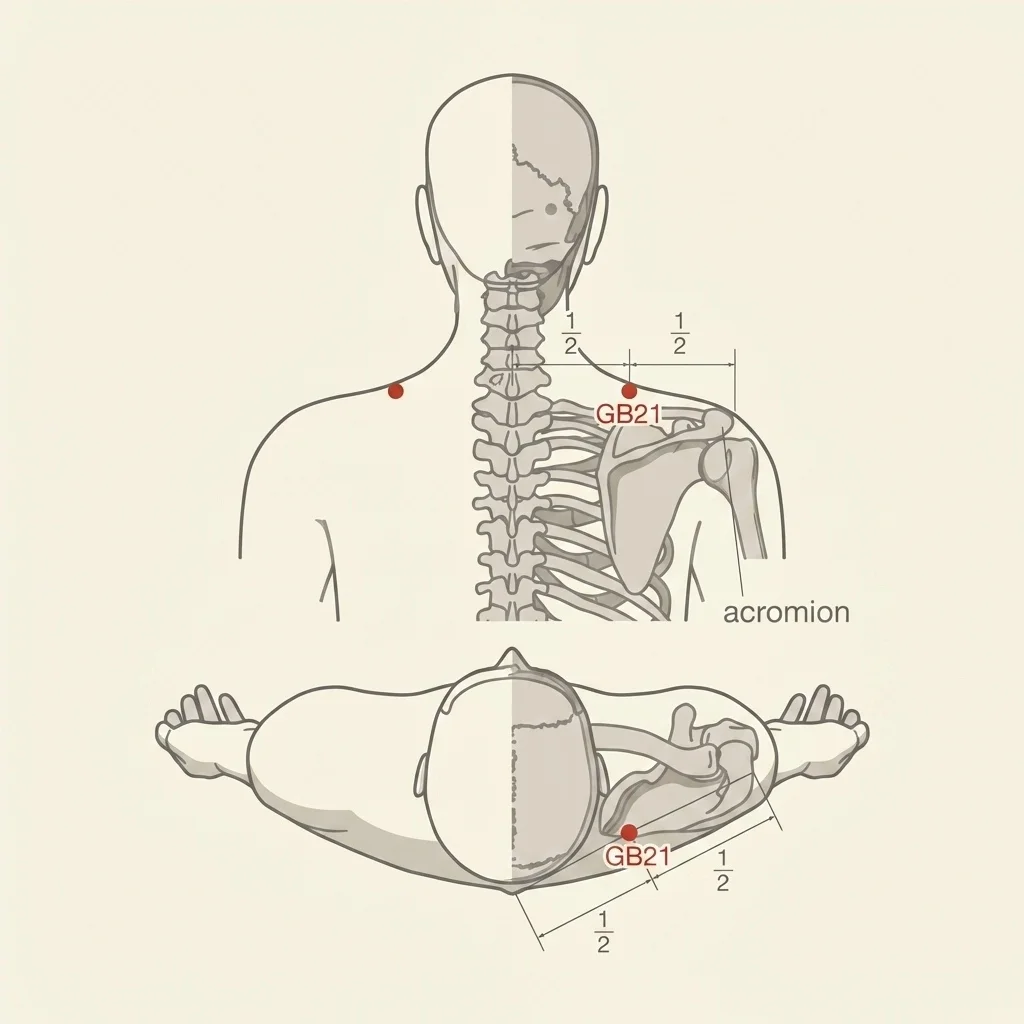
We add electroacupuncture at GB21, SI11, BL17 for thoracic segmental modulation.
Specific Postural Guidance for Breastfeeding
Postural correction during breastfeeding is an essential part of treatment — without it, acupuncture treats the consequence but not the cause of the overload. When implemented, the recommendations below can help reduce the overload that favors new trigger point formation.
- Raise the baby to breast height (firm nursing pillow) instead of bending the trunk downward — the breast goes to the baby, not the other way around
- Bilateral arm support (chair armrests, lateral pillows) to avoid sustained isometric contraction of the deltoids and trapezius
- Vary the breastfeeding position (cradle, side-lying, football hold) to distribute the load across different muscle groups
- Use a nursing chair with a reclining backrest and proper lumbar support — avoid very soft sofas that offer no spinal support
- Micro-breaks every 10 minutes to move the shoulders and neck — even during the feed, small neck rotations prevent muscle ischemia
- Avoid using a phone while breastfeeding — the extra neck flexion to look at the screen dramatically amplifies cervical overload
Myths and Facts
Myth vs. Fact
Acupuncture during breastfeeding can affect milk production
Specific data in breastfeeding women are scarce; acupuncture is considered low risk when performed by a trained physician. The available evidence shows no signal that acupuncture reduces milk production.
Back pain during breastfeeding is normal and will go away with weaning
Pain is common but not normal. Chronic trigger points do not disappear spontaneously with weaning — they may persist and even worsen without treatment, evolving into chronic cervicothoracic pain.
Acetaminophen is enough to control breastfeeding-related musculoskeletal pain
Acetaminophen has limited efficacy against pronounced myofascial pain, because it does not act directly on trigger points. Direct needling of trigger points may be a useful alternative; any medication adjustment is the attending physician's decision.
Frequently Asked Questions
Frequently Asked Questions
Yes, immediately. Acupuncture introduces no substance into the body — it is a mechanical stimulus. There is no waiting period before breastfeeding after a session.
Mastitis requires specific medical treatment (antibiotics if bacterial). Acupuncture can serve as an adjunct for mastitis pain and the thoracic pain that accompanies breast engorgement, but treating the infection comes first.
Acupuncture can begin as soon as the postpartum mother feels comfortable — generally from the 2nd–3rd week postpartum. After a cesarean section, wait for the incision to heal adequately before needling in the abdominal region.
Yes. Many acupuncture clinics that treat lactating mothers welcome the baby in the room — with a companion to care for the infant while the mother is in session. If the baby needs to feed mid-session, treatment can be paused for breastfeeding.
Treatment may relieve trigger points already formed, and correcting nursing posture tends to help reduce recurrences. Maintenance sessions during breastfeeding may be considered case by case.