The Levator Scapulae
The levator scapulae is one of the muscles most frequently affected in office workers, programmers, and prolonged users of computers and cell phones. Despite its name suggesting an exclusively scapular function, this muscle is one of the main sources of cervical pain with limitation of movement — especially the neck stiffness that prevents head rotation to one side upon waking.
The clinical pattern of the levator scapulae is só specific that patients describe it almost identically: pain at the angle between the neck and shoulder, a sensation of stiffness that prevents turning the head to one side, and sometimes a dull ache between the shoulder blades. This muscle works in synergy with the upper trapezius — frequently both are affected simultaneously.
Pain Location
Angle between the neck and shoulder, with possible radiation to the posterior shoulder and medial border of the scapula
Clinical Pattern
"Stuck neck" — painful and limited rotation to one side (the side varies with the pain pattern) upon waking or after prolonged posture
Typical Cause
Computer work with a misaligned monitor, carrying a bag on one shoulder, sleeping with an arm raised
Key Exercise
"Doorway stretch" — stretching with chin tuck and ipsilateral shoulder depression — very effective
Anatomy and Function
The levator scapulae originates from the transverse processes of C1 to C4 and descends obliquely to insert into the superomedial angle of the scapula (superior angle). Its oblique downward direction — from above to below and from medial to lateral — confers combined actions: scapular elevation, downward rotation of the glenoid, and, when the scapula is fixed, ipsilateral inclination and slight ipsilateral rotation of the cervical spine.
The levator scapulae is innervated by the dorsal scapular nerve (C4-C5) and by direct branches of the cervical plexus (C3-C4). Its close relationship with the cervical transverse processes — the site of origin — explains why dysfunction of the cervical facet joints and the MTrPs of the levator scapulae frequently coexist and are clinically confused.

Trigger Points
The levator scapulae has its main trigger point (TrP1) in the muscle belly, in the region of the posterior angle of the neck — exactly where the muscle makes the "curve" between the cervical spine and the scapula. This point is found approximately 1-2 cm above and medial to the superior angle of the scapula and is recognizable by intense local pain on palpation.
Trigger Points of the Levator Scapulae
| Point | Location | Referred Pain | Clinical Finding |
|---|---|---|---|
| TrP1 (main) | Posterior angle of the neck — 1-2 cm above the superior angle of the scapula | Intense local pain, cervical stiffness, radiation to the posterior shoulder | Limited and painful cervical rotation, to the same or the opposite side, depending on the pain pattern |
| TrP2 (secondary) | Insertion at the superior angle of the scapula | Pain at the medial border of the scapula | Sensation of "pain between the shoulder blades" |

The most characteristic clinical finding of the MTrP in the levator scapulae is painful limitation of cervical rotation. The limited rotation may be toward the same side as the affected muscle or toward the opposite side, depending on the pain pattern. This asymmetric limitation — one side free, the other restricted — is the guiding sign that distinguishes levator scapulae involvement from other patterns of cervical pain.
Referred Pain Pattern
The referred pain of the levator scapulae concentrates mainly in the ipsilateral posterior cervical region — the patient points to the angle between the neck and shoulder as the location of the pain — with possible extension to the posterior shoulder and medial border of the scapula. Unlike the upper trapezius (which refers to the temple), the levator scapulae does not generate significant headache — the pain stays localized in the lower nape and shoulder.
Pain and stiffness in the posterior and lateral neck
Limited and painful cervical rotation to one side
Sensation of "stuck neck" upon waking
Pain that radiates to the ipsilateral posterior shoulder
Dull pain at the medial border of the scapula
Worsening when carrying a bag or backpack on the affected shoulder
Worsening at the end of a day of computer work
Temporary relief with local heat and massage
Morning stiffness with limited cervical rotation — the "stuck neck on waking" — is só characteristic of the levator scapulae that many patients learn to recognize it after diagnosis: "it's that neck pain that won't turn to the left when I wake up". This clinical specificity makes diagnosis and follow-up of treatment response easier.
Causes and Risk Factors
The levator scapulae is overloaded by any activity that combines shoulder elevation with asymmetric postural maintenance. Chronic overload in office workers is particularly insidious because the muscle does not work in wide movements — it remains in low-intensity static contraction for hours.

A frequently overlooked cause is prolonged use of the cell phone with the arm extended in front of the body. When holding the phone in front of the face, the shoulder is elevated and slightly anteriorized, and the neck is anteriorized — a combination that overloads both the levator scapulae and the upper trapezius. The addition of daily hours of this posture over years explains the epidemic of cervical pain in the young population.
Diagnosis
The diagnosis is clinical, based on the characteristic symptom pattern and palpation of the muscle. The levator scapulae is palpated with the patient in lateral decubitus, arm relaxed along the body, neck slightly inclined toward the affected side (to relax the muscle). The physician identifies the taut band and the hypersensitive nodule in the inferior posterior cervical region.
Levator Scapulae Assessment
- Limited cervical rotation to one side (the same as or opposite to the affected muscle) — measured with a goniometer or by visual estimation
- Palpation of TrP1 in the posterior neck angle reproduces cervical pain
- Increased sensitivity at the superior angle of the scapula (insertion)
- Passive stretch test: rotation plus contralateral inclination reproduces muscle pain
- Strength test: isometric muscle contraction (shoulder elevation) may be painful
- Exclusion of cervical radiculopathy: negative Spurling, normal strength and reflexes
Cervical rotation range is the most useful objective parameter for monitoring progress. Rotation toward the limited side is reduced by 10°-30° relative to the normal side, improving progressively over the course of treatment. Documenting this measurement at baseline and across sessions objectively demonstrates clinical progress.
Differential Diagnosis
Cervical pain with limited rotation can have origins beyond the levator scapulae. Differential diagnosis is especially important when symptoms are intense, persistent, or accompanied by radiation to the upper limb.
Differential Diagnosis
C4-C5 Cervical Facet Arthropathy
Read more- Deep axial cervical pain
- Worsens with extension and ipsilateral rotation
- May have referral to the scapula
C4-C5 Cervical Disc Herniation
Read more- Radiation to the upper limb
- Positive Spurling sign
- Possible neurologic déficit
Upper Trapezius — TrPs
Read more- More cranial pain — up to the temple
- Associated temporal headache
- MTrP in the trapezius belly
Spasmodic Torticollis (Cervical Dystonia)
Read more- Involuntary and persistent deviation of the head
- Visible SCM hypertrophy
- Response to botulinum toxin
Spinous Angle Syndrome (Winged Scapula)
- Protrusion of the medial border of the scapula
- Serratus anterior weakness
- Long thoracic nerve injury
Levator scapulae versus upper trapezius: palpatory differentiation
Levator scapulae and upper trapezius are adjacent, synergistic muscles often affected simultaneously, making clinical differentiation difficult. The most practical distinction is by the location of referred pain: the upper trapezius refers to the temple and skull (headache), while the levator scapulae refers locally to the neck and posterior shoulder, without a significant cephalic component.
On physical examination, the upper trapezius is palpated at the upper edge of the shoulder (between neck and acromion), while the levator scapulae sits deeper and more posteromedially, near the superior angle of the scapula. Selectively provoking each muscle — pressing one and then the other — and noting which reproduces the patient's symptoms is the most reliable method of differentiation.
Levator scapulae
- Refers pain locally to the neck and posterior shoulder.
- Has no significant cephalic component.
- Sits deeper and more posteromedially, near the superior angle of the scapula.
Upper trapezius
- Refers pain to the temple and skull.
- Causes associated temporal headache.
- Is palpated at the upper edge of the shoulder, between neck and acromion.
Facet arthropathy versus myofascial syndrome of the levator
Cervical facet joint arthropathy (mainly C4-C5) produces axial cervical pain that can mimic the levator scapulae pattern. In facet arthropathy, pain typically worsens with cervical extension and rotation toward the affected side (a movement that compresses the facet), whereas in levator MTrP the side of limited rotation varies with the pain pattern; the side of rotation alone therefore does not separate the two conditions. Diagnostic and analgesic infiltration of the cervical medial branch confirms articular origin when positive.
The two conditions often coexist in patients with chronic cervical pain: articular dysfunction can reflexively activate muscle MTrPs, and chronic muscle spasm can overload the facet joints. Treatment must address both components for lasting results.
Myofascial torticollis versus cervical dystonia
Myofascial torticollis — neck "stuck" by MTrPs in the levator scapulae and SCM — has acute onset, usually tied to a clear triggering factor (sleeping in an awkward position, mild trauma, exertion), and responds rapidly to needling. Cervical dystonia (spasmodic torticollis) has progressive onset, with visible muscle hypertrophy (especially of the SCM), involuntary clonic movements, and resists simple conservative treatment. Dystonia responds to botulinum toxin and requires specialized neurologic evaluation.
Treatments
Treatment of the levator scapulae is highly effective when combined with correction of perpetuating postural factors. The "doorway stretch" — popular name for the specific stretch of the levator scapulae — is one of the simplest and most effective exercises in cervical myofascial medicine.
Acute Phase — "Stuck Neck" (0-3 days)
Local moist heat for 20 minutes 3-4x daily. Avoid abrupt head movements. Anti-inflammatory if needed. Gentle ischemic pressure on TrP1. Gentle passive stretching within pain tolerance.
Active Treatment (1-6 weeks)
Medical acupuncture / dry needling 1-2x per week. Specific stretches ("doorway stretch"). Workstation ergonomic correction. Strengthening of the deep cervical flexors.
Recurrence Prevention (maintenance)
Daily home stretching program. Permanent ergonomic adjustments. Assessment of bags, backpacks, and postural habits. Periodic maintenance sessions if needed.

Do
- Practice the "doorway stretch" regularly, the specific stretch for the levator scapulae.
- Center the computer monitor directly in front of the eyes.
- Apply local moist heat for 20 minutes, 3-4 times daily, in the acute phase.
Avoid
- Make abrupt head movements in the acute phase.
- Carry a bag or backpack on only one shoulder.
- Use a lateral screen that forces sustained cervical rotation.
- Treatment of the levator scapulae is highly effective when combined with correction of perpetuating postural factors.
- The "doorway stretch" is one of the simplest and most effective exercises in cervical myofascial medicine.
Acupuncture and Dry Needling
Medical acupuncture for the levator scapulae uses points that anatomically correspond to the muscle and its insertion, plus distal points for cervical pain modulation. The point SI-14 (Jianwaishu) — located 3 cun lateral to the spinous process of T1 — is the acupuncture point that most frequently coincides with the TrP1 of the levator scapulae, making it the primary treatment point.
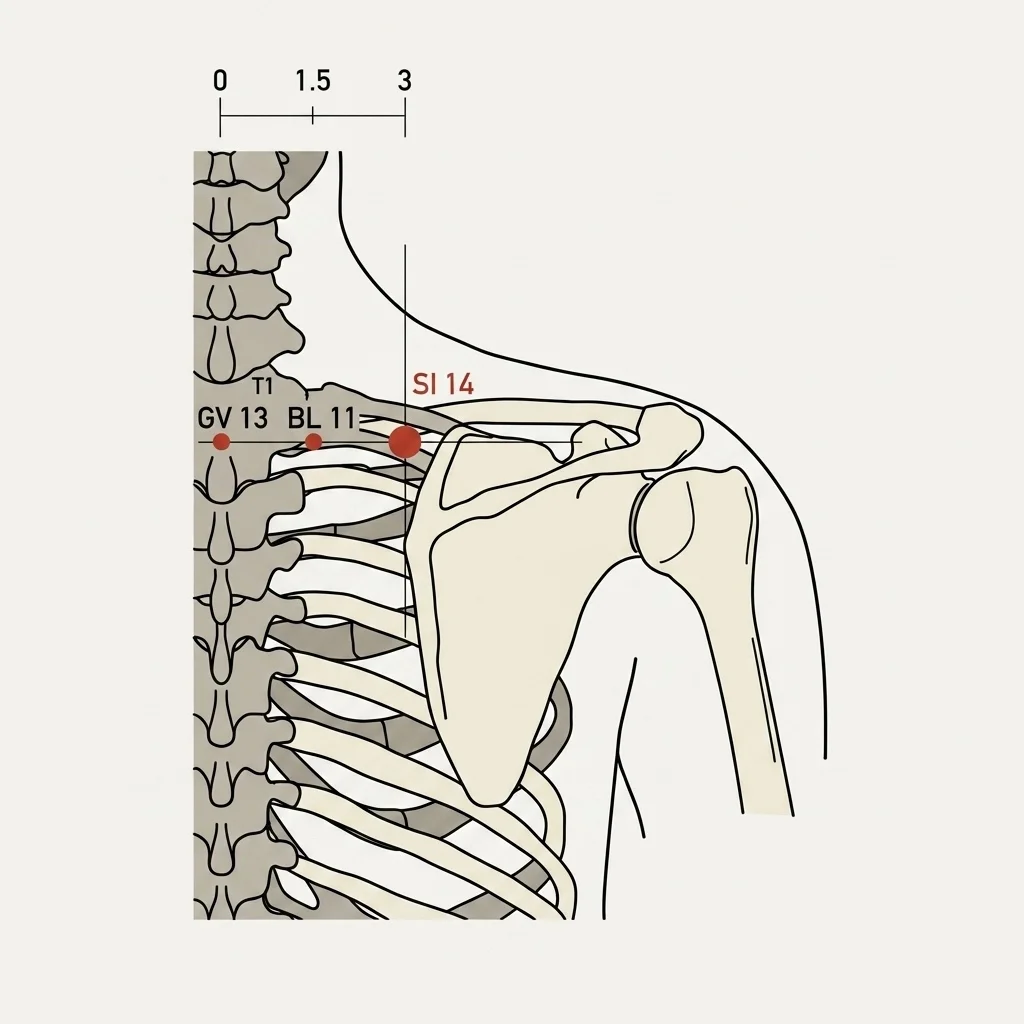
- Location
- On the back, 3 cun lateral to the inferior border of the spinous process of the first thoracic vertebra (T1).
Myth vs. Fact
A stuck neck on waking will get better on its own without treatment.
Acute episodes of myofascial torticollis of the levator scapulae often improve spontaneously in 2-5 days. However, without treating the perpetuating factors (posture, ergonomics), recurrences are frequent and become progressively more frequent and intense. Treating an acute episode with acupuncture accelerates recovery and offers the opportunity to correct the causes and prevent recurrences.
Pain at the neck angle always means a cervical spine problem.
Many episodes of pain at the neck angle with limited rotation have a myofascial component — specifically from the levator scapulae and upper trapezius — although a joint (facet) origin is also common and may coexist. Structural problems (disc herniation, advanced cervical osteoarthritis) are distinguished by radiation to the upper limb, neurologic deficits, and MRI findings.
Prognosis
The prognosis of MTrPs of the levator scapulae is excellent. Acute episodes respond in 1-3 sessions of medical acupuncture. Chronic cases with persistent and multiple MTrPs require 4-8 sessions. Long-term success depends on correcting postural factors and maintaining the stretches.
Patients who learn the "doorway stretch" and practice it regularly have much lower recurrence rates. The most impactful ergonomic change — centering the computer monitor directly in front of the eyes — often solves the problem on its own in workers who spend many hours at the screen.
When to Seek Medical Help
Frequently Asked Questions
Levator Scapulae: Common Questions
The "stuck neck on waking" is almost always caused by acute activation of trigger points in the levator scapulae (and frequently in the upper trapezius as well). This occurs when the muscle remains in shortening for hours during sleep — lateral position with too high a pillow, sleeping prone with cervical rotation, or arm raised under the head. The muscle, on waking, is in spasm and resistant to stretching.
Yes. "Levator scapulae" is the Latin name for the muscle, equivalent to the descriptive English term "scapula elevator" (or in Portuguese, "elevador da escápula" / "levantador da escápula"). In medical literature and clinical practice, the terms are used interchangeably. The muscle is also popularly called the "neck angle" by patients, who instinctively indicate its location when describing the pain.
The ideal pillow keeps the cervical spine neutral — aligned with the thoracic spine — regardless of sleep position. Side sleepers need a pillow that fills the space between shoulder and ear (usually higher and firmer). Back sleepers need a lower pillow that maintains the natural cervical lordosis. The general principle: avoid pillows that are too high (forcing cervical flexion) or too low (forcing extension).
Yes, especially when the backpack is carried on only one shoulder. The loaded side contracts the levator scapulae continuously to keep the shoulder from being pulled down by the weight. With daily use for hours, this static contraction progressively activates trigger points. The most effective solution is a two-strap backpack that distributes weight equally. When using a shoulder bag, alternate sides regularly.
Yes, with key ergonomic adjustments: center the monitor directly in front of the eyes (avoid lateral screens that force sustained cervical rotation), raise the monitor só the top of the screen sits at eye level, use armrests or forearm supports to reduce static shoulder load, and take 5-minute breaks every hour for cervical and scapular stretches.
For acute torticollis (less than 1 week), 1-3 sessions are usually enough for complete resolution. For chronic cervical pain with persistent MTrPs, the typical protocol is 4-8 sessions at 1-2 per week. When perpetuating factors are well identified and corrected, the prognosis is excellent even in chronic cases.
Yes, it is one of the most effective stretches in cervical myofascial medicine. Combining chin tuck (chin retraction), lateral inclination to the opposite side, and slight downward chin rotation places the muscle at maximum length, stretching the taut bands and reflexively inhibiting spasm. Regular practice of this levator-specific stretch may help relieve cervical pain and improve rotation, although direct evidence is limited.
Rarely, and indirectly. The referred pain pattern of the levator scapulae concentrates in the posterior cervical region and shoulder, without significant extension to the skull. Unlike the upper trapezius (which causes temporal headache) and the suboccipitals (which cause occipital and diffuse frontal headache), the levator typically does not produce headache. When headache accompanies cervical pain, other muscles should be investigated.
Yes. The levator scapulae shares with the upper trapezius the role of "stress muscle": when feeling anxiety, tension, or fear, people reflexively elevate the shoulders — simultaneous contraction of the upper trapezius and levator. In people under chronic stress, this tonic coactivation is practically continuous during waking hours, progressively activating MTrPs. Stress management is part of definitive treatment in this group.
Yes, especially adolescents with heavy school backpacks, long periods using a cell phone or tablet in poor posture, and students who spend hours at the computer. Prevention in children and adolescents includes: a two-strap backpack carrying no more than 10 to 15% of body weight, postural awareness, and regular breaks during study. Treatment in young people prioritizes postural correction and stretching.
Related Reading
Deepen your knowledge with related articles