What Is Hyperemesis Gravidarum?
Hyperemesis gravidarum (HG) is the most severe form of the spectrum of nausea and vomiting in pregnancy. It is characterized by intractable vomiting that leads to dehydration, weight loss (more than 5% of pregestational weight), electrolyte disturbances, and ketonuria. It affects 0.3-3% of pregnant women.
It differs from common morning sickness (which affects 70-80% of pregnant women) in severity, persistence, and need for medical treatment. HG generally begins between 4-7 weeks of gestation, peaks at 8-12 weeks, and in most cases resolves by 20 weeks. However, 10-20% of women have symptoms until delivery.
The impact is devastating: repeated hospitalizations, work disability, social isolation, depression, and in extreme cases, termination of a desired pregnancy. HG is one of the leading causes of first-trimester hospitalization.
Dehydration and Ketonuria
Intractable vomiting leads to dehydration, electrolyte disturbances, and starvation ketosis, requiring intravenous hydration.
Emotional Impact
Depression, anxiety, and post-traumatic stress are common. Many women report HG as the worst experience of their lives.
Treatable
With adequate antiemetics, hydration, and nutritional support, most pregnant women recover well without harm to the fetus.
Pathophysiology
The exact cause of HG remains incompletely understood, but recent advances have identified GDF15 (growth differentiation factor 15) as the central mediator. GDF15 is produced by the placenta at increasing levels in the first trimester and acts on GFRAL receptors in the brainstem, in the área postrema — the vomiting center.
Susceptibility to HG depends not only on GDF15 levels, but on individual sensitivity to the hormone. Women with low prior exposure to GDF15 (low baseline levels before pregnancy) show greater sensitivity when levels rise abruptly in pregnancy, explaining interindividual variability.

hCG (human chorionic gonadotropin) contributes indirectly by stimulating thyroid production (transient gestational hyperthyroidism) and possibly modulating GDF15 secretion. Risk factors include multiple pregnancy, hydatidiform mole, female fetal sex, family history of HG, and HG in a previous pregnancy.
Symptoms
HG symptoms differ from common morning sickness in intensity, persistence, and metabolic consequences. Clinical distinction is essential for adequate management.
Morning Sickness vs Hyperemesis Gravidarum
| Feature | Morning Sickness | Hyperemesis Gravidarum |
|---|---|---|
| Prevalence | 70-80% of pregnant women | 0.3-3% of pregnant women |
| Weight loss | Absent or minimal | > 5% of pregestational weight |
| Dehydration | Absent | Present, with ketonuria |
| Food tolerance | Maintains intake, with restrictions | Inability to retain food/liquids |
| Duration | Up to 12-16 weeks in most | May persist until delivery |
| Hospitalization | Rarely necessary | Frequently necessary |
Severity Signs
Intractable vomiting
Inability to retain any food or liquid for more than 24 hours.
Significant weight loss
More than 5% of pregestational weight. In severe cases, may exceed 10%.
Signs of dehydration
Dry mucosa, tachycardia, postural hypotension, reduced urinary output.
Ptyalism (sialorrhea)
Excessive saliva production, often impossible to swallow, extremely uncomfortable.
Intense psychological impact
Depression, suicidal ideation, isolation, sense of medical abandonment — require active attention.
Diagnosis
HG diagnosis is clinical, based on persistent vomiting with weight loss > 5%, dehydration, and ketonuria in the first half of pregnancy, after excluding other causes. Laboratory tests confirm severity and guide replacement.
Laboratory Evaluation
- Complete blood count: hemoconcentration (elevated hematocrit from dehydration)
- Electrolytes: hyponatremia, hypokalemia, hypochloremia
- Renal function: creatinine may rise from dehydration
- Urinalysis: ketonuria, elevated specific gravity
- Thyroid function: suppressed TSH and elevated free T4 (transient gestational hyperthyroidism in 60%)
- Ultrasound: rule out molar and twin pregnancy
Differential Diagnosis
Acute Gastroenteritis
- Acute onset with associated diarrhea
- Frequent fever
- Not exclusive to pregnancy
- High fever
- Blood in stools
PC-6 (Neiguan) for nausea control regardless of etiology
Cholecystitis
- Pain in the right upper quadrant after fatty meals
- Possible jaundice
- Fever and leukocytosis
- High fever and chills — cholangitis
Adjuvant in nausea control; does not treat cholecystitis
Acute Pancreatitis
- Intense epigastric pain in a band
- Nausea and vomiting with predominant abdominal pain
- Elevated amylase and lipase
- Intense abdominal pain — medical emergency
Not indicated in the acute phase; may help in recovery
Peptic Ulcer
- Epigastric pain on an empty stomach or at night
- History of NSAID use
- Not exclusive to pregnancy
- Hematemesis — upper gastrointestinal bleeding
PC-6 and ST-36 for dyspeptic symptoms; coordinated with the obstetrician
Psychogenic Nausea
- Nausea associated with stressful situations
- No significant weight loss
- Improvement in relaxation contexts
May be considered as support for nausea with an anxious component; limited evidence
Acute Gastroenteritis
Acute gastroenteritis is easily confused with hyperemesis gravidarum because of the intense nausea and vomiting. The key clinical difference is diarrhea in gastroenteritis — absent in hyperemesis — along with fever and no relationship to the hormonal progression of pregnancy.
Investigating urinary infection is important, since pyelonephritis may present with intense vomiting in pregnancy. Urine culture should be obtained in every pregnant woman with vomiting and fever. The PC-6 (Neiguan) point has modest evidence for nausea — it may be used as an adjunct by the physician acupuncturist while the etiologic workup continues.
Cholecystitis and Pancreatitis
Hepatobiliary diseases are more common in pregnancy due to changes in bile composition and gallbladder motility. Gestational cholecystitis and pancreatitis can present with intense vomiting similar to hyperemesis, but usually come with specific abdominal pain — right upper quadrant in cholecystitis, and a band radiating to the back in pancreatitis.
Measuring amylase, lipase, transaminases, and bilirubins, combined with abdominal ultrasound, distinguishes these conditions. They require urgent hospital management and should not be confused with simple hyperemesis gravidarum.
Psychogenic Nausea
Nausea with a strong anxiety component may be worsened in pregnancy by the combination of hormonal changes, insecurities, and routine disruptions. The distinction is clinical: psychogenic nausea tends to be situational, without the characteristic progression of hyperemesis and without ketosis or electrolyte imbalance.
Medical acupuncture may be considered as support in this context, aiming to relieve both the nausea and the associated anxiety, although the specific evidence is limited.
Treatment
HG treatment is stepped, starting with dietary measures and first-line antiemetics, progressing to higher-potency antiemetics and nutritional support based on severity. Intravenous hydration is essential in moderate to severe cases.
First Line
Pyridoxine (vitamin B6) + doxylamine, ginger, dietary changes (small frequent meals, avoiding olfactory triggers). Ondansetron 4-8 mg if no response.
Intravenous Hydration
Saline solution or lactated Ringer with thiamine (vitamin B1) — always before glucose infusion to prevent Wernicke encephalopathy. Potassium replacement according to levels.
Second-Line Antiemetics
Metoclopramide (10 mg every 8 h), promethazine, dimenhydrinate. Corticosteroids (methylprednisolone) for refractory cases after 10 weeks.
Nutritional Support
Enteral nutrition by nasogastric tube in refractory cases. Total parenteral nutrition as a last resort due to complication risks (thrombosis, catheter infection).
Do
- Eat small, frequent meals
- Start antiemetic treatment early, before the cycle of dehydration and ketosis that worsens vomiting takes hold
- Seek medical evaluation when nausea and vomiting prevent adequate intake of liquids or food for more than 24 hours
Avoid
- Expose yourself to olfactory triggers
- Wait for it to "improve on its own"
- Rely only on crackers and ginger: they may help with mild nausea but are insufficient for true HG
- HG treatment is stepped, starting with dietary measures and first-line antiemetics.
- Intravenous hydration is essential in moderate to severe cases.
- Total parenteral nutrition is a last resort due to complication risks.
Acupuncture as Treatment
Acupuncture and acupressure — especially at the PC-6 (Neiguan) point on the inner surface of the wrist — are investigated for nausea and vomiting in pregnancy. PC-6 is the point with the greatest research volume for antiemetic effect in medicine, also studied in postoperative and chemotherapy-induced nausea.
The proposed mechanism involves modulation of the nucleus of the solitary tract and the área postrema in the brainstem via vagal and median afferents. PC-6 stimulation may reduce central emetic activity by releasing beta-endorphins and modulating serotonergic neurotransmission.
Systematic reviews show variable results. Acupressure at PC-6 (anti-nausea wristbands) has modest evidence for mild to moderate nausea. For severe HG, the evidence is insufficient to recommend acupuncture as standalone treatment, but it may be useful as an adjuvant to standard antiemetic treatment. The safety profile in pregnancy is favorable.
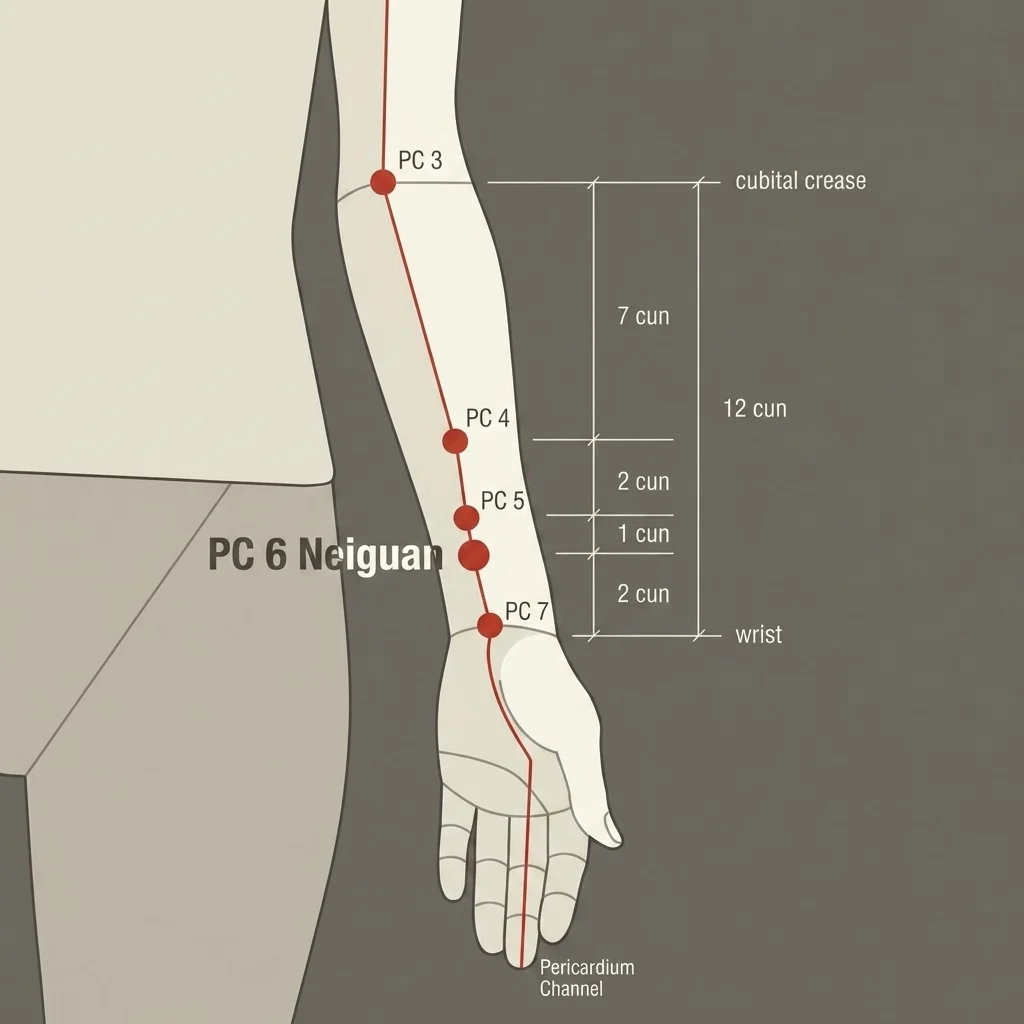
Point on the inner surface of the wrist. It is the point with the greatest research volume for antiemetic effect in medicine.
Prognosis
With adequate treatment, the maternal and fetal prognosis of HG is good in most cases. Most pregnant women improve significantly by 20 weeks. There is no consistent evidence of increased fetal malformations associated with HG or the antiemetics used.
However, severe and prolonged HG is associated with lower birth weight, prematurity, and long-term maternal psychological complications. The recurrence risk in subsequent pregnancies is 15-80%, depending on the severity of the previous episode.
Myths and Facts
Myth vs. Fact
Hyperemesis is just exaggerated morning sickness
HG is a serious medical condition that may cause dehydration, malnutrition, electrolyte disturbances, and hospitalization. It is qualitatively different from common morning sickness.
It is psychological — the woman does not want the pregnancy
HG has a physiologic basis (GDF15, hCG, genetic factors). Most affected women deeply want the pregnancy and suffer emotionally from the condition.
Antiemetics in pregnancy cause malformations
Doxylamine/pyridoxine, ondansetron, and metoclopramide have a favorable safety profile in pregnancy. The risk of not treating (dehydration, malnutrition) is generally greater than the risk from the medications.
Just eating crackers and ginger improves it
These measures may help with mild nausea but are insufficient for true HG. Minimizing the condition's severity delays adequate treatment and increases suffering.
When to Seek Help
Pregnancy nausea and vomiting that prevent adequate intake of liquids or food for more than 24 hours require medical evaluation. Do not wait for it to "improve on its own."
Frequently Asked Questions
Morning nausea and vomiting affect 70-80% of pregnant women and are self-limited (improving after 12-14 weeks). Hyperemesis gravidarum is the severe form — intractable vomiting, weight loss above 5%, dehydration, and ketonuria — affecting 0.3-3% of pregnant women and often requiring hospitalization.
The physician acupuncturist primarily uses the PC-6 (Neiguan) point, and proposed mechanisms include modulating gastric motility, reducing intestinal serotonin release, and stimulating vagal pathways that inhibit nausea. Systematic reviews, including the Cochrane review, show variable results, with modest, limited-quality evidence for PC-6 acupressure in mild to moderate nausea of pregnancy. For severe HG, acupuncture does not replace the antiemetic treatment and hydration prescribed by the obstetrician.
Yes, when performed by a physician acupuncturist with obstetric experience. Some points are contraindicated in pregnancy (SP-6, LI-4, BL-67 at stimulating doses). PC-6 and nausea-specific points are considered safe. Acupuncture does not replace rehydration and nutritional support in severe cases.
For mild to moderate nausea, initial results usually appear after 2-3 sessions. The usual protocol is 30-40-minute sessions, 2 to 3 times a week during the first 12-14 weeks. Acupressure at PC-6 (acupressure wristbands) can complement treatment between sessions.
When adequately treated, hyperemesis gravidarum generally does not cause significant fetal harm. Severe untreated forms with severe malnutrition may be associated with fetal growth restriction. Wernicke encephalopathy from thiamine deficiency is the most serious and preventable maternal complication.
Pyridoxine (vitamin B6) combined with doxylamine is the first-line pharmacologic treatment, with an established safety profile. Metoclopramide and ondansetron may be used in refractory cases. Corticosteroids are reserved for severe cases. All medications should be prescribed by the obstetrician.
It may help as a complement. The Cochrane review on nausea and vomiting in pregnancy found limited and inconsistent evidence for PC-6 acupressure and for acupuncture, with no clear benefit over placebo. The safety profile is favorable, and acupressure can be added to usual care for mild to moderate nausea. In hyperemesis gravidarum, the mainstay is hydration, electrolyte replacement, and antiemetics prescribed by the obstetrician; acupuncture does not replace them.
Hospitalization is indicated for clinical dehydration, weight loss above 5% of pregestational weight, ketonuria, inability to maintain oral hydration, or significant electrolyte alterations. Intravenous hydration, thiamine, and parenteral antiemetics form the basis of hospital treatment.
Yes. The recurrence risk in subsequent pregnancies is 15-80%, depending on the severity of the previous episode. Starting interventions early (dietary, acupuncture, vitamin B6 supplementation) from the beginning of the next pregnancy may reduce severity.
The obstetrician is the primary professional managing hyperemesis gravidarum. The physician acupuncturist may be added to care to complement nausea control, especially in mild to moderate cases. In severe cases with dehydration, hospital management is mandatory.