What Is Labor Pain?
Labor pain is a complex sensory and emotional experience that accompanies the physiologic process of birth. It is considered one of the most intense forms of pain that human beings can experience, with intensity comparable to fractures and amputations on pain scales.
Unlike other forms of pain, labor pain is physiologic — it does not indicate a pathologic lesion. It involves visceral and somatic mechanisms that differ by phase of labor, with progressive shifts in transmission pathways. Pain perception is modulated by psychological, cultural, hormonal, and prior-experience factors.
Adequate labor pain management is essential for maternal and fetal well-being. Uncontrolled severe pain activates the hypothalamic-pituitary-adrenal axis, releasing catecholamines that may compromise uteroplacental flow and slow labor progression.
Visceral and Somatic Pain
The first stage involves visceral pain (cervical dilation). The second stage adds somatic pain (perineal distension). The neural pathways are distinct.
Endogenous Modulation
Labor activates the endogenous opioid system, releasing beta-endorphins that naturally modulate pain perception.
Multidimensional Impact
Labor pain has sensory, affective, cognitive, and behavioral components. Management should address all dimensions.
Pathophysiology
In the first stage of labor (dilation), the pain is predominantly visceral. It originates from distension and contraction of the lower uterine segment and from cervical dilation. Nociceptive impulses are transmitted by visceral afferent fibers that accompany the sympathetic nerves, entering the spinal cord at the T10-L1 levels.
In the second stage (expulsion), somatic pain is added, caused by distension of the vagina, perineum, and pelvic structures by fetal descent. This pain is transmitted by the pudendal nerve (S2-S4), being more acute, localized, and intense than the visceral pain of the first stage.
The endogenous pain modulation system is activated during labor. Beta-endorphins increase progressively during labor. Endogenous oxytocin also has a central analgesic effect. This system explains why many women tolerate the pain without pharmacologic analgesia.
Pain Pathways in the Stages of Labor
| Stage | Type of Pain | Origin | Neural Pathway |
|---|---|---|---|
| First stage — latent | Visceral, diffuse, cramping | Cervical dilation (0-6 cm) | T11-T12 (sympathetic fibers) |
| First stage — active | Intense visceral, referred | Cervical dilation (6-10 cm) | T10-L1 (sympathetic fibers) |
| Second stage | Acute somatic, localized | Vaginal and perineal distension | S2-S4 (pudendal nerve) |
| Third stage | Mild to moderate visceral | Postpartum uterine contractions | T10-L1 |
Pain Features
Labor pain is dynamic and progressive. Its intensity, location, and quality change as labor advances. Individual perception is influenced by factors such as parity, fetal position, prior preparation, and emotional support.
Pain Patterns in Labor
Low back pain during contractions
Present in 30-40% of laboring women. More common when the fetus is in the occiput-posterior position. Pain refers to the sacral region via shared dermatomes.
Suprapubic and lower abdominal pain
Visceral pain typical of cervical dilation. Initially diffuse, becomes more intense and localized as dilation progresses.
Pelvic and rectal pressure
Intense pressure sensation in the pelvis and rectum, particularly in the active phase and transition. Indicates descent of the fetal presentation.
Perineal pain in the second stage
Acute, well-localized somatic pain caused by perineal distension. Intense burning sensation during crowning.
Pain referred to thighs and inguinal region
T10-L1 dermatomes project referred pain to the inner thighs, inguinal regions, and flank. Typical pattern of the advanced first stage.
Intervals of relief between contractions
Contractions are intermittent, allowing periods of rest. In the latent phase, intervals are long. In the active phase, they shorten progressively.
First stage
- The pain is predominantly visceral
- It originates from distension and contraction of the lower uterine segment and from cervical dilation
- It is transmitted by visceral afferent fibers entering the spinal cord at the T10-L1 levels
- It is diffuse, cramping, radiating to the low back
Second stage
- Somatic pain is added
- It is caused by distension of the vagina, perineum, and pelvic structures by fetal descent
- It is transmitted by the pudendal nerve (S2-S4)
- It is more acute, localized, and intense than the visceral pain of the first stage
Pain Assessment
Assessment of labor pain should be continuous and multidimensional. The visual analog scale (VAS) is useful to quantify intensity but does not capture affective and cognitive components. The decision about analgesia should consider the laboring woman wishes, the labor stage, and available resources.
Assessment and Monitoring
Source: WHO and NICE
Intensity Assessment
- Visual analog scale (0-10) during and between contractions
- Laboring woman's behavior (facial expression, vocalization, posture)
- Ability to communicate and relax between contractions
- Impact on her ability to cooperate and use coping techniques
Factors Influencing Perception
- Parity (nulliparas generally report more intense pain)
- Fetal position (occiput-posterior increases low back pain)
- Use of exogenous oxytocin (may intensify contractions)
- Prenatal preparation and expectations about birth
Safety Monitoring
- Fetal cardiotocography during analgesia
- Maternal vital signs (BP, HR), especially with epidural
- Labor progression during analgesia
- Sensory block level when neuraxial analgesia is used
Differential Diagnosis
False Labor
- Irregular and non-progressive contractions
- Without progressive cervical dilation
- Cease with ambulation or hydration
Acupuncture may help manage associated anxiety and discomfort
Placenta Previa
- Painless vaginal bleeding
- Uterus generally non-tender
- Diagnosis by ultrasonography
- Heavy bleeding — obstetric emergency
Contraindicated in the acute phase; no specific indication
Placental Abruption
- Constant and intense abdominal pain
- Rigid and tender uterus on palpation
- Vaginal bleeding (may be concealed)
- Acute fetal distress
- Maternal shock
Obstetric emergency — no role for acupuncture in the acute phase
Uterine Rupture
- Acute abdominal pain with sudden cessation of contractions
- Maternal hemodynamic instability
- History of prior cesarean
- Absolute surgical emergency
Surgical emergency — no role for acupuncture
Amniotic Infection (Chorioamnionitis)
- Maternal fever during labor
- Fetal tachycardia
- Foul-smelling amniotic fluid
- High fever
- Fetal distress
Requires immediate antibiotic therapy; acupuncture has no role in treatment
False Labor
False labor (prodromal labor) is the most common condition to differentiate from true labor pain. Contractions are irregular in frequency and intensity, do not increase progressively, and do not cause cervical dilation. They stop spontaneously with ambulation, warm bath, or hydration.
Serial cervical examination (1-2 hour intervals) is the most reliable method to differentiate. True labor shows progressive dilation. Acupuncture may help manage anxiety and discomfort during this uncertain period, keeping the woman calm and well hydrated until active labor is confirmed.
Placental Abruption
Placental abruption is an obstetric emergency that may present with intense abdominal pain in late pregnancy. Unlike labor pain, abruption pain is constant (no relief intervals), the uterus becomes rigid and hypertonic, and vaginal bleeding may occur (although bleeding is concealed in up to 20% of cases).
Any intense, persistent abdominal pain in the third trimester should be evaluated immediately by the obstetric team. Early recognition is critical for maternal and fetal survival.
Placenta Previa
Placenta previa typically causes painless vaginal bleeding in the third trimester, without associated abdominal pain. The absence of pain is the main differentiator from labor. Diagnosis is confirmed by ultrasonography.
The obstetric team must know the diagnosis before any intervention in labor. Acupuncture has no role in placenta previa management, and vaginal examination is contraindicated in these cases.
Treatment
Analgesia options in labor range from non-pharmacologic methods to neuraxial analgesia. Epidural analgesia remains the gold standard for severe pain, but there is growing evidence for complementary methods that can be used alone or in combination.
Non-Pharmacologic Methods
Free movement, warm immersion bath, birthing ball, low-back massage, breathing techniques, continuous doula support. TENS (transcutaneous electrical stimulation) applied to the lumbar region. These measures activate the descending pain modulation system.
Inhalational Analgesia
50% nitrous oxide (Entonox), self-administered by the laboring woman during contractions. Rapid, short-duration effect. Can be combined with other methods. Availability varies by region.
Neuraxial Analgesia
Epidural or combined spinal-epidural analgesia. A catheter is placed in the epidural space with continuous infusion or bolus of local anesthetic and opioid. Excellent relief and preserved mobility at low doses. Satisfaction rate > 90%.
Systemic Opioids
Intravenous meperidine, fentanyl, or remifentanil. Partial relief with side effects (nausea, sedation). Remifentanil PCA offers the best profile among systemic opioids. Neonatal depression is possible with meperidine.
- Analgesia options in labor range from non-pharmacologic methods to neuraxial analgesia.
- Epidural analgesia remains the gold standard for severe pain.
- There is growing evidence for complementary methods that can be used alone or in combination.
Acupuncture as Treatment
Acupuncture is one of the complementary therapies studied for labor pain, with possible benefit and evidence of variable quality. The mechanism involves activation of the endogenous opioid system, with release of enkephalins and beta-endorphins at the spinal and supraspinal levels, modulating nociceptive transmission in labor pathways.
Points such as LI-4 (Hegu), SP-6 (Sanyinjiao), BL-32 (Ciliao), and GB-21 (Jianjing) are the most used. BL-32, located at the second sacral foramen, is a point used for low back pain during contractions, with a proposed mechanism of modulating sacral afferent input.
Clinical trials with electroacupuncture at LI-4 and SP-6 have described reduced pain scores and, in some studies, less need for epidural analgesia or oxytocin — with heterogeneity across protocols and populations. The anxiolytic effect of acupuncture may help reduce the affective component of pain, helping break the fear-tension-pain cycle.
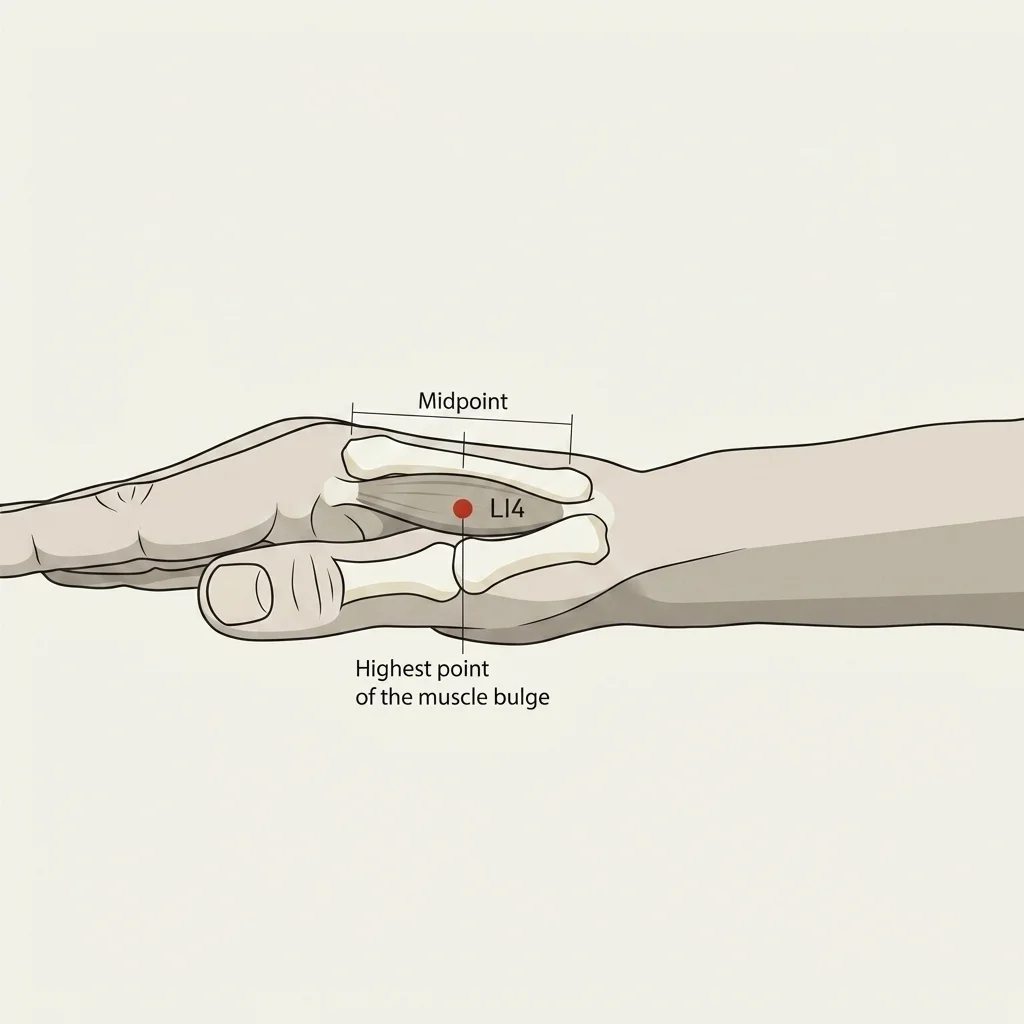
- Location
- On the radial aspect of the hand, between the first and second metacarpal bones, closer to the second metacarpal and approximately at its midpoint — corresponds to the apex of the muscular bulge when the thumb and index finger are brought together.
Prognosis
Labor pain is self-limited and resolves with birth. Satisfaction with the birth experience does not correlate directly with pain intensity, but rather with the sense of control, the support received, and respect for the laboring woman's choices.
Inadequate pain management may have lasting consequences. A traumatic childbirth experience is associated with increased risk of postpartum depression, post-traumatic stress disorder, and tokophobia in future pregnancies. Adequate pain management is therefore an investment in maternal mental health.
Myths and Facts
Myth vs. Fact
Labor pain is necessary and beneficial.
Although labor pain is physiologic, intense uncontrolled pain produces adverse effects: excessive catecholamine release, reduced uteroplacental flow, and maternal exhaustion. Adequate analgesia may improve obstetric outcomes.
Myth vs. Fact
Epidural always slows labor and causes cesarean.
Meta-analyses show that epidural analgesia may slightly prolong the second stage of labor (on average 15-30 minutes), but does not increase the cesarean rate. Early epidural (before 4 cm) is as safe as late epidural.
Myth vs. Fact
Acupuncture has no real efficacy in labor pain.
Systematic reviews with thousands of laboring women suggest that acupuncture may reduce pain scores and the need for pharmacologic analgesia — with variable evidence quality across studies. The proposed mechanisms (endogenous opioid modulation, spinal afferents) are supported by neurophysiologic studies, although incompletely understood.
When to Seek Help
Frequently Asked Questions
Labor pain is among the most intense known because it combines visceral pain (cervical dilation, via T10-L1) with somatic pain (perineal distension, via S2-S4). Anticipation and fear also amplify perception by activating the stress axis. However, the body activates compensatory mechanisms — beta-endorphins increase progressively during labor.
The medical acupuncturist uses points such as LI-4 (Hegu), SP-6 (Sanyinjiao), and BL-32 (Ciliao) to activate the endogenous opioid system, releasing enkephalins and beta-endorphins. This modulates nociceptive transmission in spinal and supraspinal pathways, and also reduces anxiety and the affective component of pain.
For most laboring women, acupuncture is useful as a complement to epidural in severe pain, not a substitute. It may be considered as a complementary measure for women who want birth with minimal pharmacologic intervention and for latent-phase pain relief, with uncertain benefit. The decision should be individualized and respected.
Ideally, start acupuncture for birth preparation in the last 4 weeks of pregnancy (from 36 weeks), with weekly sessions. This familiarizes the laboring woman with the treatment; preparation should be agreed in advance with the obstetrician, and a benefit on cervical ripening has not been established. During labor, acupuncture can be applied in a single continuous session as needed.
Systematic reviews with thousands of laboring women suggest a favorable safety profile for mother and fetus during labor, when performed by a medical acupuncturist with obstetric experience and coordinated with the team. Serious adverse events are rare but not absent — as with any needle intervention (hematoma, syncope, infection). Points such as SP-6 should be used cautiously outside the labor context, since they may stimulate contractions.
Meta-analyses show that epidural may slightly prolong the second stage of labor (on average 15 to 30 minutes), and does not increase the rate of cesarean; across all trials instrumental delivery increased, an effect not seen in more recent studies. Early epidural (before 4 cm) is as safe as late epidural. The pain-control benefit outweighs the impact on progression.
In the first stage, pain is visceral (cervical dilation), diffuse, cramping, radiating to the low back, and transmitted by the T10-L1 segments. In the second stage, somatic pain from perineal distension is added — acute, well localized, and transmitted by the pudendal nerve (S2-S4). The two have distinct qualities and respond differently to each analgesia method.
Grantly Dick-Read described the fear-tension-pain cycle: fear amplifies pain perception, which generates more tension and muscle resistance, which in turn increases pain. Prenatal preparation, continuous emotional support, and acupuncture can break this cycle, reducing the affective component of pain.
Yes. Intense uncontrolled labor pain is associated with increased risk of postpartum depression, post-traumatic stress disorder (PTSD), and tokophobia (extreme fear of future births). Adequate pain management is an investment in maternal mental health, not just immediate comfort.
Plan in advance, preferably during prenatal care, with a medical acupuncturist experienced in obstetrics. Inform the obstetrician and hospital team about the wish to use acupuncture during labor to ensure adequate support.
Related Reading
Deepen your knowledge with related articles