Electroacupuncture
Main result
−0.16ms
Improvement in median nerve latency (verum)
Change within the treated group
Blinded, placebo-controlled RCT · Brain · Maeda et al. · 2017 · 80 participants
Rewiring the primary somatosensory cortex in carpal tunnel syndrome with acupuncture
Weak
Limited
Moderate
Strong
- Local acupuncture28 participants
- Distal acupuncture28 participants
21.3 %
Symptom reduction (verum)
25.1 %
Sustained improvement at 3 months (verum)
Study design sheet
- n=80 participants
- High impact
- Design
- Blinded, placebo-controlled RCT
- Participants
- 80
n = 80; median of studies with the same design: 79
- Duration
8 weeks of treatment with 3-month follow-up
16 sessions over 8 weeks
- Groups
Each band is proportional to the group’s number of participants, in the order of the list below. - Local acupuncture (28)Electroacupuncture on the most affected hand
- Distal acupuncture (28)Electroacupuncture at the contralateral ankle
- Sham (23)Non-penetrating needles without stimulation
- OBJECTIVE
- To investigate the neuroplastic mechanisms of acupuncture in carpal tunnel syndrome through neuroimaging
- WHO
- 80 patients with mild/moderate carpal tunnel syndrome (65 women, mean age 49 years)
- POINTS
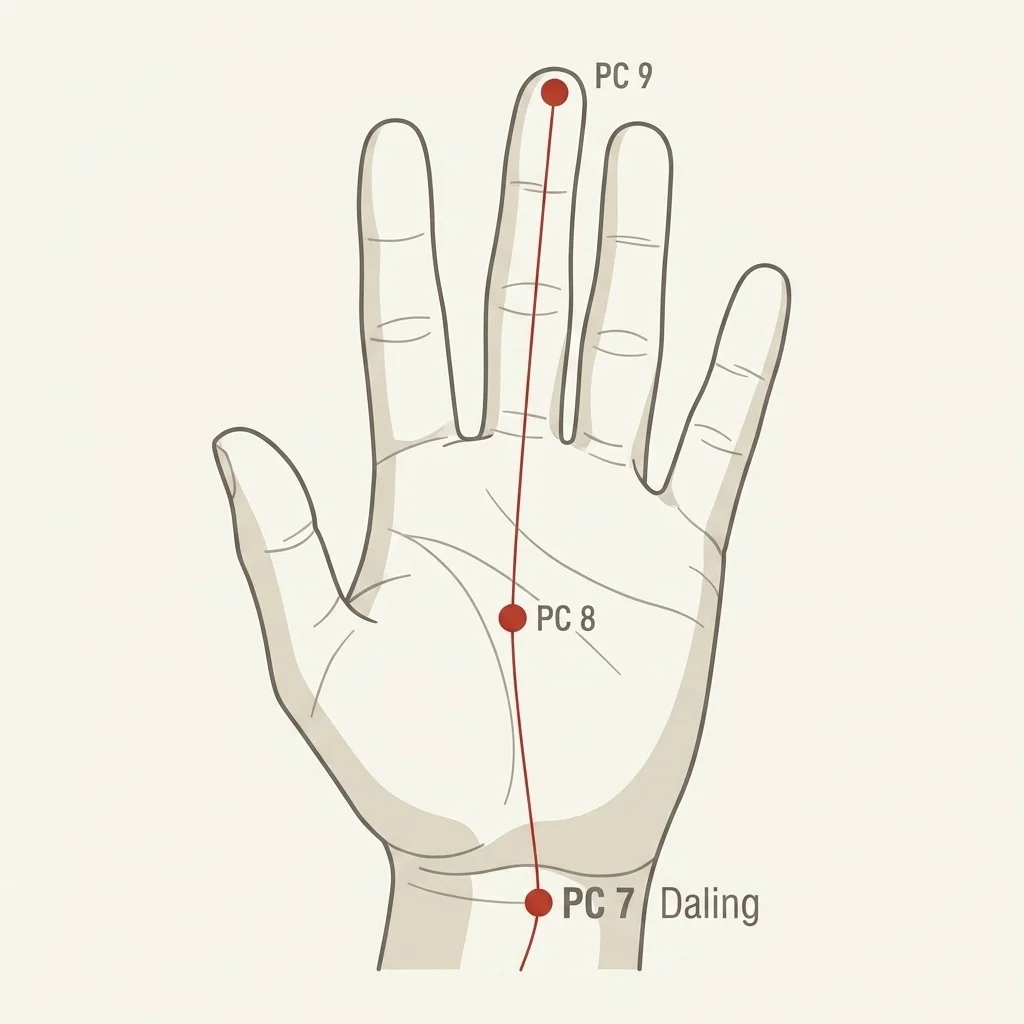
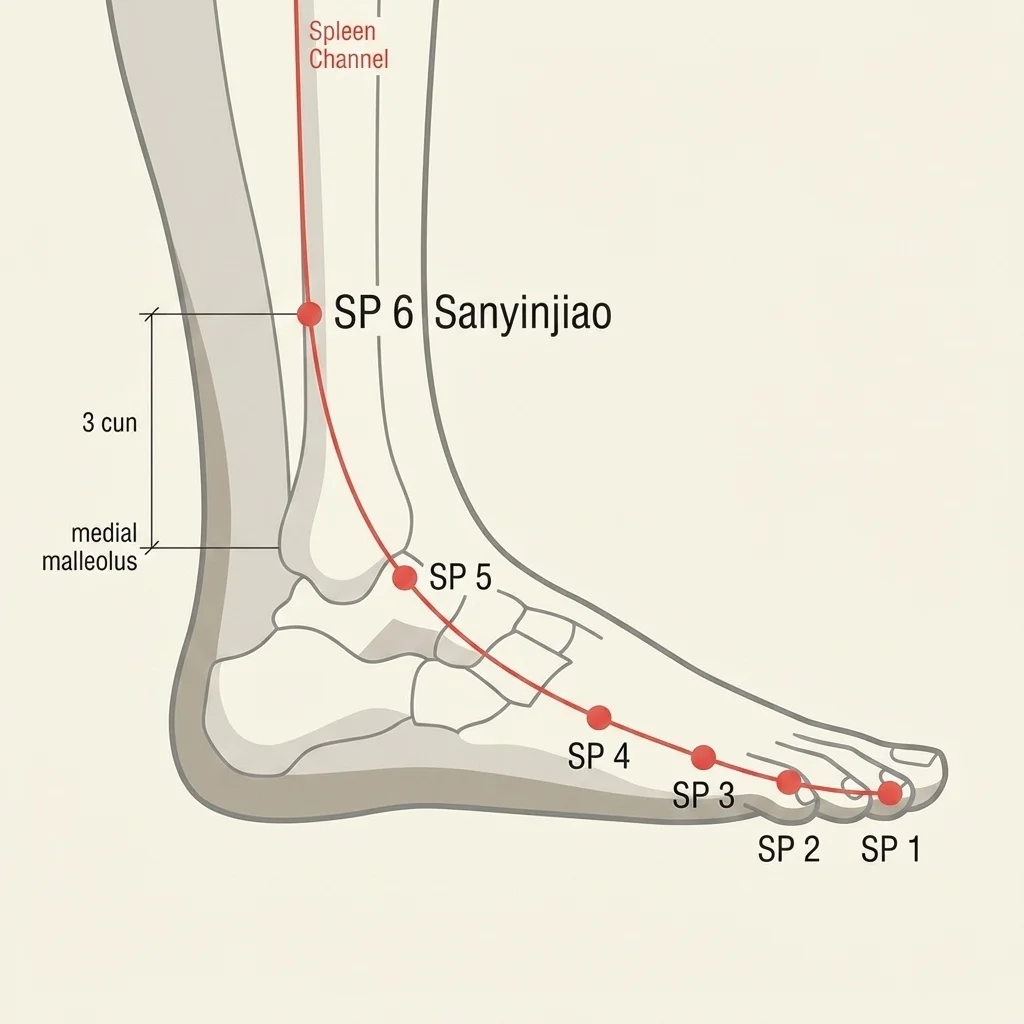
- Local: TE-5, PC-7 with electrical stimulation; Distal: SP-6, LR-4 with electrical stimulation
- Results in numbers
- −0.16 msImprovement in median nerve latency (verum)
- 21.3 %Symptom reduction (verum)
- 25.1 %Sustained improvement at 3 months (verum)
- 1.8 mmIncrease in D2/D3 cortical separation
- Outcome comparison
- Symptom reduction post-treatment
- Verum acupuncture: 21.3 of 100
- Sham: 22.7 of 100
- Sustained improvement at 3 months
- Verum acupuncture: 25.1 of 100
- Sham: 11.1 of 100
- Symptom reduction post-treatment
What does this mean for you?
In this study, true and sham acupuncture reduced carpal tunnel syndrome symptoms similarly right after treatment, but only true acupuncture objectively improved nerve function and reorganized the brain. The brain improvements may predict which patients will have lasting symptom relief.
Article summary
Plain-language narrative summary
This randomized controlled trial represents a milestone in understanding the neurologic mechanisms of acupuncture for carpal tunnel syndrome (CTS). Researchers at Massachusetts General Hospital conducted a sophisticated clinical trial combining clinical evaluations, nerve conduction studies, and advanced neuroimaging to investigate how acupuncture affects both the peripheral and central nervous systems. Carpal tunnel syndrome is the most common compressive neuropathy, affecting the median nerve at the wrist, and prior studies had already demonstrated that this condition causes not only local nerve problems but also alterations in the organization of the primary somatosensory cortex (S1). Eighty patients with mild to moderate CTS were randomized into three groups: local electroacupuncture on the most affected hand (points TE-5 and PC-7), distal electroacupuncture at the contralateral ankle (points SP-6 and LR-4), or sham acupuncture with non-penetrating needles.
Treatment consisted of 16 sessions over 8 weeks, followed by assessments at 3 months. The protocol included 2 Hz electrical stimulation at the main points and manual stimulation at additional points individually chosen by the acupuncturists. The results revealed fascinating findings about the mechanisms of acupuncture action. Although both true and sham acupuncture reduced symptoms immediately after treatment (21.3% vs 22.7%, respectively), only true acupuncture produced measurable objective improvements.
Specifically, true acupuncture significantly improved median sensory nerve conduction latency (-0.16 ms), whereas the sham group did not significantly change latency (+0.12 ms; P=0.28). Even more striking, functional neuroimaging showed that true acupuncture increased the separation between cortical representations of digits 2 and 3 in the somatosensory cortex, indicating beneficial brain reorganization. This finding is particularly meaningful because CTS causes abnormal overlap of these brain representations, and acupuncture appears to reverse this maladaptive reorganization. One of the most clinically relevant findings was that improvements in brain organization immediately after treatment predicted which patients would maintain symptom relief at 3 months.
Patients who showed greater increase in D2/D3 cortical separation had more sustained symptom reduction. Diffusion tensor imaging analysis revealed distinct mechanisms for local versus distal acupuncture. Both modalities improved median nerve function but through different neuroplastic pathways in the brain. Local acupuncture was associated with white matter microstructure changes adjacent to the hand area in the ipsilateral somatosensory cortex, whereas distal acupuncture affected the leg area.
This suggests that different acupoints activate somatotopically specific pathways in the brain. At 3-month follow-up, true acupuncture maintained significant symptom reduction (25.1%), whereas the sham group showed only a trend toward improvement (11.1%). This difference was statistically significant, demonstrating lasting benefits specific to true acupuncture. The study has several important limitations.
Participants were unblinded after the post-treatment assessment, which may have influenced long-term results. In addition, the neuroimaging analyses were not corrected for multiple regional comparisons. The sample size for some subgroup analyses was also limited because of technical issues and dropouts. The clinical implications are substantial.
The study provides objective evidence that true acupuncture differs from placebo in producing measurable physiologic changes in both the peripheral nerve and the brain. This is relevant for debates over whether acupuncture is more than an elaborate placebo effect. The ability to predict long-term outcomes through measures of brain neuroplasticity opens possibilities for personalized medicine in acupuncture.
Strengths
- Randomized controlled design with three well-defined groups
- Use of multiple assessment modalities (clinical, electrophysiologic, neuroimaging)
- Standardized treatment protocol with long-term follow-up
- Neuroplastic findings that predict clinical outcomes
- Sophisticated analysis of somatotopic-specific mechanisms
Limitations
- Early unblinding of participants after treatment
- Reduced sample size for some neuroimaging analyses
- Lack of correction for multiple regional comparisons in DTI
- Limitations in interpreting white matter changes
- Follow-up limited to only 3 months

Expert Commentary
Clinical Relevance
Carpal tunnel syndrome occupies a substantial share of the physiatry and pain clinic, and the therapeutic decision among splinting, injection, physical therapy, and surgery often leaves a window open for adjuvant interventions. What this work from the Harvard group brings concretely to practice is the objective documentation, via nerve conduction studies, of improvement in median nerve conduction latency with true acupuncture — an outcome that goes beyond self-reported pain. For the clinician evaluating patients with mild to moderate CTS who do not yet have a clear surgical indication, or who are awaiting a long orthopedic queue, this represents an option with measurable physiologic substrate. The population studied was patients with mild to moderate CTS; the paper does not evaluate subgroups such as pregnant patients, those who decline injection, or those at high surgical risk. Maintenance of symptomatic improvement at 25.1% at three months reinforces that the effect is not ephemeral, qualifying acupuncture as a legitimate component of conservative management.
Notable Findings
The most robust finding of this trial is not symptomatic reduction itself — after all, the sham group also improved immediately — but the objective divergence in electrophysiologic behavior: while true acupuncture reduced sensory latency by 0.16 ms, the sham group did not significantly change latency (+0.12 ms; P=0.28). This difference of nearly 0.3 ms in conduction latency was statistically significant between groups (P=0.02) and is difficult to attribute to expectation alone. Equally noteworthy is the functional neuroimaging finding: a 1.8 mm increase in cortical somatotopic separation between digits 2 and 3 in S1. CTS produces maladaptive overlap of these representations; acupuncture appears to reverse this phenomenon, and the magnitude of this reversal predicts who will maintain improvement at three months. The fact that local and distal acupuncture activate somatotopically distinct neuroplastic pathways — white matter adjacent to the hand area versus the leg area — suggests mechanistic specificity that goes well beyond a nonspecific response to stimulation.
From My Experience
In my musculoskeletal pain clinic practice, mild to moderate CTS is probably the compressive neuropathy in which I have the most experience with adjuvant acupuncture. I usually observe the first signs of response between the third and fifth session — reduction of nocturnal tingling and improvement of tactile sensation in the digits — and on average I work with cycles of 10 to 12 sessions to consolidate the result. What this article empirically confirms is something I have noticed for years: patients who respond quickly in the first weeks tend to maintain the gain. I almost always combine this with a home tendon and nerve gliding program, and recommend night splint use during the cycle. Patients with severe CTS or established motor conduction block I do not refer for acupuncture as primary treatment — I refer them for surgery and use acupuncture postoperatively. The 2 Hz electroacupuncture protocol described by the authors is consistent with what I use; low frequencies favor endogenous beta-endorphin release and, in the context of neuropathy, appear to have a more pronounced peripheral regenerative effect than high frequencies.
Dr. Marcus Yu Bin Pai · MD, PhD · Pain Medicine · Physical Medicine and Rehabilitation · Medical Acupuncture
PhD in Health Sciences, University of São Paulo. Board-certified in Pain Medicine, Physical Medicine and Rehabilitation, and Medical Acupuncture.
- 1Upper LimbPC 7
- 1Lower LimbSP 6
See the numbers: Where the cited points are
| Region | Points | Codes |
|---|---|---|
| Upper Limb | 1 | PC 7 |
| Lower Limb | 1 | SP 6 |
Points cited
Full original article
Read the full scientific study
Brain · 2017
DOI: 10.1093/brain/awx015
CITED IN · 1 PAGE
This study underpins the editorial content of the site.
Condition pages and clinical articles that cite this evidence as the basis of their recommendations.
Scientific review
 Dr. Marcus Yu Bin Pai
Scientific lead · CRM-SP 158074 · RQE 65523 · 65524 · 655241
Medical disclaimer: This content is for educational purposes only and does not replace consultation, diagnosis, or treatment by a qualified professional. Some information may be assisted by artificial intelligence and is subject to inaccuracies. Always consult a physician.
Content reviewed by the medical team at CEIMEC — Integrated Centre for Chinese Medicine Studies, a reference in Medical Acupuncture for over 30 years.
- Strong
- Moderate
- Limited
- Weak
See the numbers: This study among the Library’s studies
| Study design | Electroacupuncture | All studies |
|---|---|---|
| Meta-analysis · Systematic Review | 21 | 387 |
| RCT | 26 | 224 |
| Clinical Guideline | 1 | 5 |
| Observational | 0 | 38 |
| Case Series | 1 | 7 |
| Narrative Review | 8 | 155 |
| Preclinical / Animal | 4 | 6 |
| Other | 24 | 203 |
Related articles
Based on this article’s categories
Sridhar et al. · Communications Medicine · 2026
- Chronic Pain
- Electroacupuncture
- Mechanisms of Action
Ulett et al. · Biological Psychiatry · 1998
- Electroacupuncture
- Mechanisms of Action
Park et al. · Journal of Inflammation Research · 2018
- Electroacupuncture
- Mechanisms of Action
Zhou et al. · Biomedicine & Pharmacotherapy · 2023
- Electroacupuncture
- Chronic Pain
- Mechanisms of Action