Anatomy & Point Location
Main result
4.0cm
Needle insertion depth
Journal of Acupuncture and Meridian Studies · Leow et al. · 2017 · 1 participants
Ultrasonography in Acupuncture Uses in Education and Research
Weak
Limited
Moderate
Strong
1.8 cm
Calculated perpendicular depth
1.85 cm
Depth verified by ultrasound
Study design sheet
- Case Study
- n = 1 participant
- Proof of Concept
- Participants
- 1
- Duration
Single procedure
Single procedure
- Groups
- Participant (1)Ultrasound-guided acupuncture at BL-32
- OBJECTIVE
- Explore the use of ultrasound to locate acupuncture points and quantify needle insertion depth
- WHO
- One member of the research team as a volunteer
- POINTS
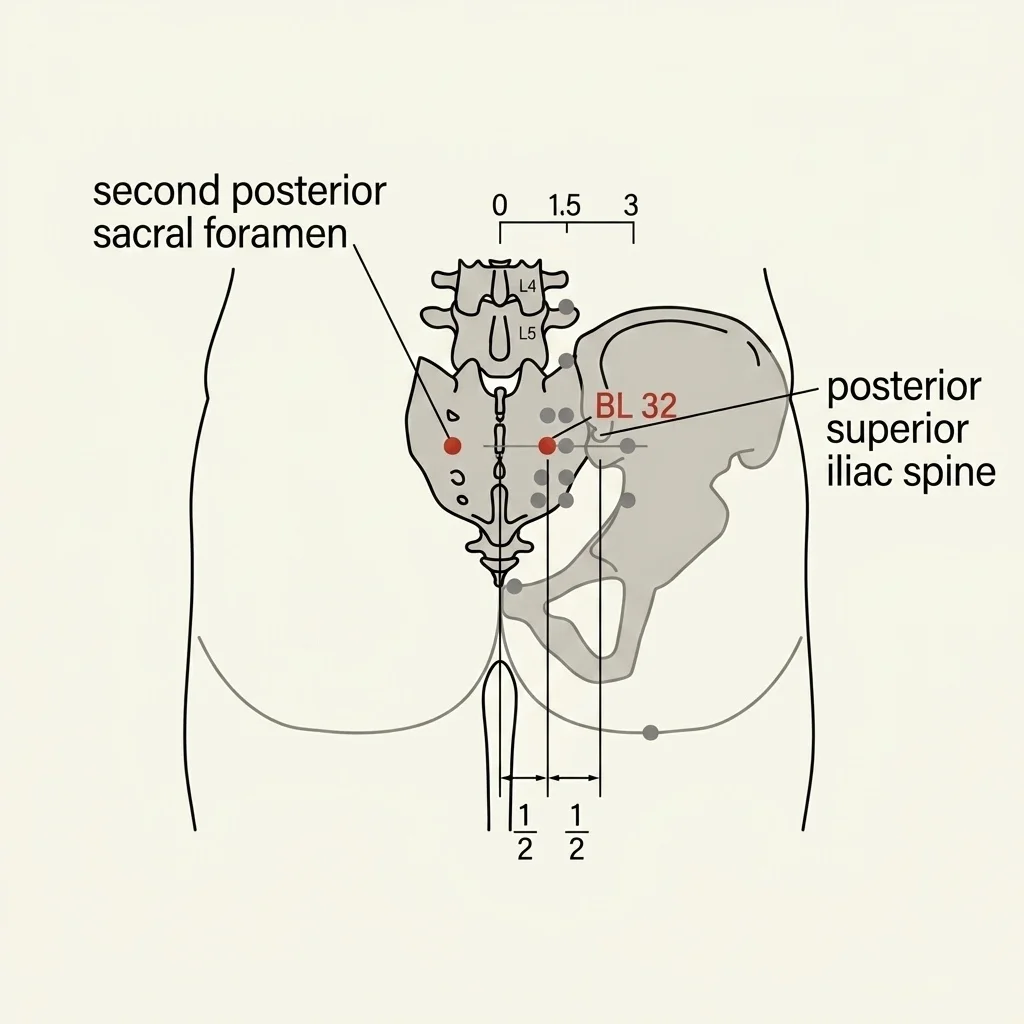
- BL-32 (Ciliao) — second posterior sacral foramen
- Results in numbers
- 4.0 cmNeedle insertion depth
- 1.8 cmCalculated perpendicular depth
- 1.85 cmDepth verified by ultrasound
- 30°Insertion angle
- Outcome comparison
- Perpendicular depth (cm)
- Calculated (Pythagoras): 1.8 of 4
- Measured (Ultrasound): 1.85 of 4
- Perpendicular depth (cm)
What does this mean for you?
This study, in a single participant, suggested that ultrasound can be used to locate the acupuncture point and estimate the needle insertion depth. This may help standardize treatment, especially at deep points such as those in the sacrum.
Article summary
Plain-language narrative summary
The present study represents an important advance in the pursuit of greater precision and standardization in acupuncture practice, an ancient therapy that traditionally relies on the practitioner's experience and the patient's subjective sensation. Conducted in Singapore, this case report explored how ultrasonography can be used to locate acupuncture points with greater precision and to determine the appropriate depth for needle insertion, using as a model the BL-32 point, located at the second posterior sacral foramen.
Acupuncture faces significant challenges related to the precise location of points and the determination of correct insertion depth. Traditionally, practitioners locate points through palpation and determine whether the needle has reached the appropriate depth through the patient's report of "de qi"—a sensation of numbness, tingling, or heaviness indicating adequate stimulation. However, this approach is subjective and can vary considerably across patients and practitioners. Traditional manuals present significant variations in depth recommendations, reaching differences of up to 50% for the same point, which can compromise treatment efficacy.
The researchers developed a four-step experimental protocol to assess the utility of ultrasonography in acupuncture. First, a certified practitioner located the BL-32 point through traditional palpation, using anatomical landmarks such as the posterior superior iliac spine. Next, they used an ultrasound device to visualize the anatomical structures around the point and measure the distance from the skin to the sacral foramen. In the third step, an acupuncture needle was inserted at a 30-degree angle while the study participant reported the sensations experienced.
Finally, a new ultrasound examination confirmed the needle's position and its proximity to the desired sacral foramen.
The results demonstrated that ultrasonography was able to clearly visualize all relevant anatomical structures, from the skin to the sacral bone, including the gluteus maximus muscle and ligaments. The distance from the skin to the sacral foramen was measured at 2.1 cm on both sides of the participant. During needle insertion, the participant reported the first sensation of "de qi" when the needle reached 3.5 cm depth, still within the gluteus muscle. A more intense sensation was experienced at 4.0 cm, when the needle effectively reached the surface of the sacral foramen.
Using mathematical calculations based on the Pythagorean theorem, considering the 30-degree insertion angle, the researchers estimated a perpendicular depth of 1.8 cm, which was confirmed by ultrasonography with notable precision at 1.85 cm.
These findings have important implications for both clinical practice and acupuncture education. For patients, this means more precise and potentially more effective treatments, especially in people with greater amounts of adipose tissue, where locating deep points can be more challenging. Sacral foramen points such as BL-32 are particularly important in the treatment of urological, digestive, reproductive, and pelvic pain problems, but they are frequently underused due to the difficulty of precise location. With the assistance of ultrasonography, these points can be used with greater confidence and safety.
For novice practitioners, this technology offers a valuable learning tool, allowing real-time visualization of anatomy and confirmation of correct needle positioning.
In the research arena, ultrasonography can contribute significantly to the standardization of treatment protocols, a critical need for rigorous scientific studies on acupuncture. The ability to objectively quantify insertion depth and confirm precise needle placement can improve the quality and reproducibility of research in this field. In addition, visualization of nearby vascular structures may increase procedural safety, although vascular complications are extremely rare in acupuncture.
It is important to recognize the limitations of this study. It was conducted in only one participant, which limits the generalizability of the results to different body types and individual anatomical variations. The study focused exclusively on the BL-32 point, although the principles may be applicable to other points. The need for ultrasound equipment and specialized training may limit practical applicability in all clinical contexts.
Future studies with larger samples and various acupuncture points are needed to fully validate this approach.
In conclusion, this case report suggests the promising potential of ultrasonography as a complementary tool in acupuncture practice, offering greater precision, safety, and objectivity to a therapy traditionally based on subjective experience. Although more studies are needed, these results pave the way for a productive integration between modern technology and traditional medicine.
Strengths
- Innovative method to standardize acupuncture
- Real-time visualization of structures
- Precise mathematical calculations
- Potential to improve safety
Limitations
- Only one participant
- Tested at only one point
- Proof-of-concept study
- Requires validation in a larger sample
Expert Commentary
Clinical Relevance
Ultrasound applied to acupuncture solves a concrete problem that every medical acupuncturist recognizes: the variability in insertion depth for anatomically complex points. BL-32, located at the second posterior sacral foramen, is indispensable in the management of chronic pelvic pain, urologic dysfunctions, and gynecologic conditions, but adequate stimulation requires that the needle reach the proximity of the foramen—not merely the overlying gluteus muscle. The ultrasound confirmation that the perpendicular depth calculated mathematically (1.8 cm) coincided with direct measurement (1.85 cm) provides an objective basis for calibrating insertion in patients with increased subcutaneous tissue, in whom palpation of bony landmarks becomes imprecise. This approach has direct application in pain services with obese or post-surgical patient profiles, where procedural safety and protocol reproducibility are priorities.
Notable Findings
The most clinically relevant aspect of this work is the dissociation between the first sensation of de qi, obtained at 3.5 cm—still in the gluteus maximus muscle—and effective stimulation of the sacral foramen, which occurred at 4.0 cm. This empirically demonstrates that the patient's subjective sensation is not a sufficient indicator of correct needle positioning at deep points, contradicting a historically accepted operational premise. The application of the Pythagorean theorem to calculate perpendicular depth from the 30° insertion angle and the linear depth inserted provides a simple, reproducible, and equipment-independent mathematical tool—broadening its utility even in contexts without available ultrasound. The convergence between geometric calculation and sonographic measurement confers conceptual robustness on the method.
From My Experience
In my practice at the Pain Center of HC-FMUSP, BL-32 is a routine component of protocols for lumbosacral pain, dysmenorrhea, and overactive bladder, and for decades we have dealt with anatomical heterogeneity among patients. I have observed that the therapeutic response in these cases tends to appear between the third and fifth session, with protocols typically running eight to twelve sessions for clinical stabilization. What this work formalizes is something experienced physicians already compensate for intuitively—adjusting angle and depth according to body type. With patients with elevated body mass index, I usually increase the insertion angle and go deeper than the standard reference of classical manuals, precisely because the bulky gluteus displaces the tactile reference. The didactic potential of ultrasound in medical training in acupuncture is, for me, the most enduring gain of this work: seeing in real time where the needle is changes the learning curve definitively.
Prof. Dr. Hong Jin Pai · PhD in Sciences, University of São Paulo
Specialist physician in Medical Acupuncture. Adjunct Professor at the Institute of Orthopedics, HC-FMUSP. Coordinator of the Acupuncture Group at the HC-FMUSP Pain Center.
- 1BackBL 32
See the numbers: Where the cited points are
| Region | Points | Codes |
|---|---|---|
| Back | 1 | BL 32 |
Points cited
Full original article
Read the full scientific study
Journal of Acupuncture and Meridian Studies · 2017
DOI: 10.1016/j.jams.2017.03.001
Scientific review
 Dr. Marcus Yu Bin Pai
Scientific lead · CRM-SP 158074 · RQE 65523 · 65524 · 655241
Medical disclaimer: This content is for educational purposes only and does not replace consultation, diagnosis, or treatment by a qualified professional. Some information may be assisted by artificial intelligence and is subject to inaccuracies. Always consult a physician.
Content reviewed by the medical team at CEIMEC — Integrated Centre for Chinese Medicine Studies, a reference in Medical Acupuncture for over 30 years.
- Strong
- Moderate
- Limited
- Weak
See the numbers: This study among the Library’s studies
| Study design | Anatomy & Point Location | All studies |
|---|---|---|
| Meta-analysis · Systematic Review | 4 | 387 |
| RCT | 7 | 224 |
| Clinical Guideline | 0 | 5 |
| Observational | 2 | 38 |
| Case Series | 1 | 7 |
| Narrative Review | 5 | 155 |
| Preclinical / Animal | 0 | 6 |
| Other | 21 | 203 |
Related articles
Based on this article’s categories
Ma et al. · Alimentary Pharmacology and Therapeutics · 2012
- Gastrointestinal Disorders
- Clinical Trial Methodology
- Anatomy & Point Location
Dorsher · Medical Acupuncture · 2008
- Anatomy & Point Location
- Clinical Trial Methodology
Lim S · Evidence-based Complementary and Alternative Medicine · 2010
- Anatomy & Point Location
- Clinical Trial Methodology
Sun et al. · Scientific Data · 2025
- Anatomy & Point Location
- Clinical Trial Methodology