Clinical Trial Methodology
Randomized Clinical Trial · BMC Complementary and Alternative Medicine · dos Santos Maciel et al. · 2016 · 321 participants
Comparison of the placebo effect between different non-penetrating acupuncture devices and real acupuncture in healthy subjects: a randomized clinical trial
Weak
Limited
Moderate
Strong
- Real Acupuncture45 participants
- Park Sham46 participants
p > 0.05
Between-group difference in perception
69.56% to 91.30%
Perception of real acupuncture - ST-25
69.56% to 86.95%
Perception of real acupuncture - BL-52
Study design sheet
- n=321
- High Methodological Impact
- Design
- Randomized Clinical Trial
- Participants
- 321
n = 321; median of studies with the same design: 79
- Duration
30 minutes
30 minutes per session
- Groups
Each band is proportional to the group’s number of participants, in the order of the list below. - Real Acupuncture (45)Real needle insertion for 30 min
- Park Sham (46)Device that simulates insertion without penetration
- Needle + Foam (46)Needle penetrates only adhesive foam
- Insertion and Removal (48)Real insertion followed by immediate removal
- Mixed Groups (136)Combination of real and placebo techniques
- OBJECTIVE
- Compare the efficacy of three different placebo acupuncture methods for blinding participants in studies
- WHO
- 321 healthy volunteers without pain or discomfort in the selected region
- POINTS
- ST-25 (abdomen) and BL-52 (lumbar region)
- Results in numbers
- 69.56% to 91.30%Perception of real acupuncture - ST-25
- 69.56% to 86.95%Perception of real acupuncture - BL-52
- p > 0.05Between-group difference in perception
- Similar between groupsDiscomfort intensity
- Outcome comparison
- Perception of real treatment (%)
- Real Acupuncture: 78 of 100
- Park Sham: 87 of 100
- Needle + Foam: 76 of 100
- Insertion/Removal: 82 of 100
- Perception of real treatment (%)
What does this mean for you?
This study, conducted in healthy volunteers with no prior experience of acupuncture, observed that different placebo acupuncture methods blinded participants to a similar degree in research. This means that, in this setting, the perception of having received real or simulated acupuncture did not differ significantly between groups, which is important to ensure the quality of acupuncture studies.
Article summary
Plain-language narrative summary
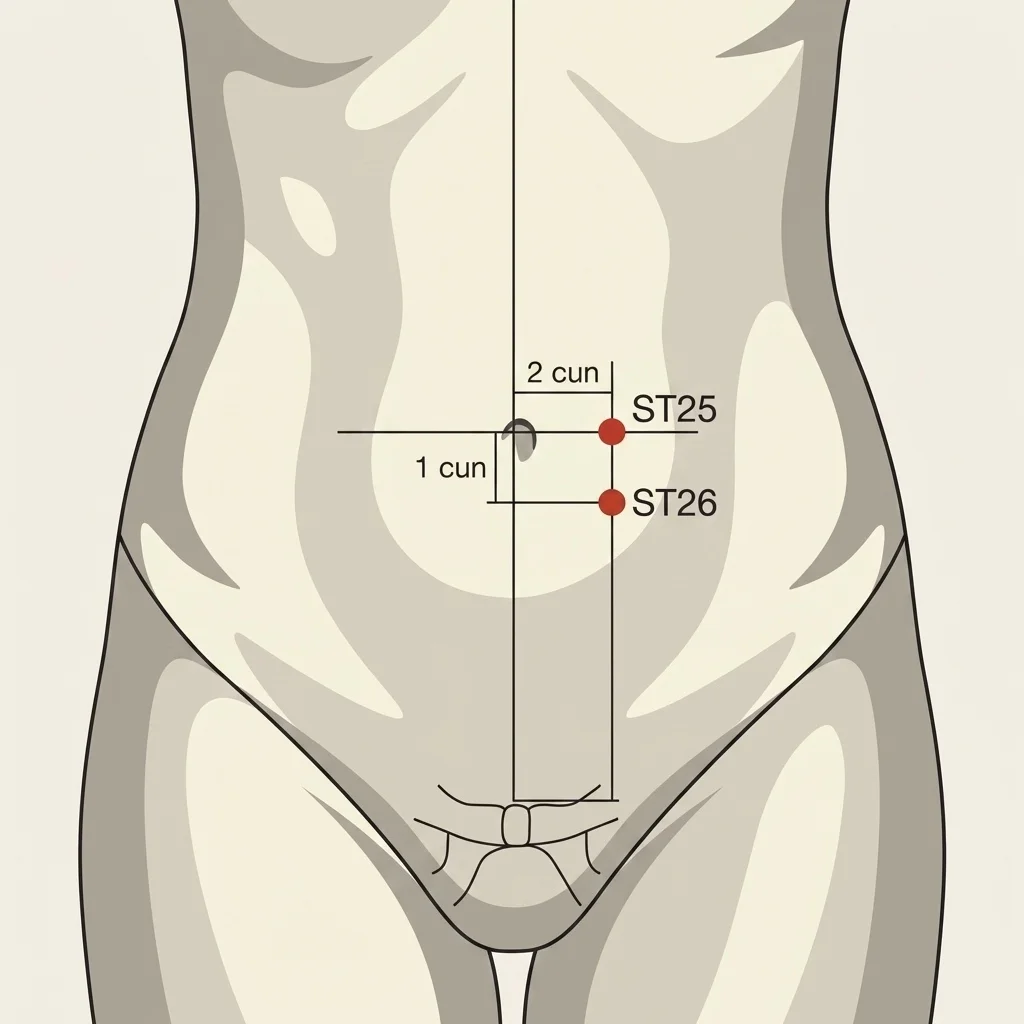
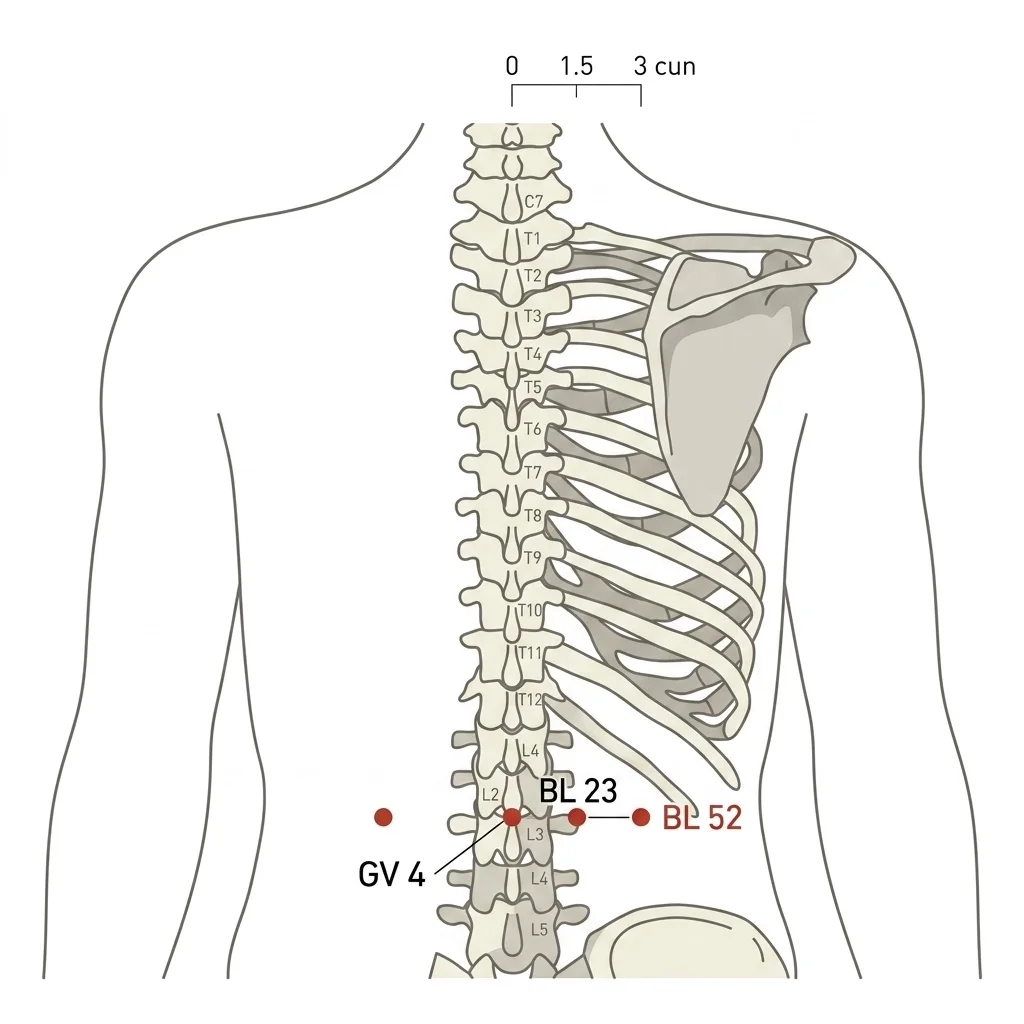
This randomized controlled trial investigated the efficacy of different placebo acupuncture methods for participant blinding in clinical trials. The research was conducted at the Federal University of Sergipe with 321 healthy volunteers, with no prior experience with acupuncture and no pain in the regions selected for application. Participants were randomized into 14 different groups, testing real acupuncture versus three distinct placebo methods: Park Sham device, adhesive foam needle technique, and insertion followed by immediate removal. Two acupuncture points were tested: ST-25 (abdominal region, 2 cun lateral to the umbilicus) and BL-52 (lumbar region, at the level of L2).
The study design was double-blind, with two investigators: one responsible for assessments (blinded to treatment) and another for application of the techniques. All procedures lasted 30 minutes, simulating a real acupuncture session. Participants were instructed not to observe the needles during the procedure. After treatment, questionnaires were administered to evaluate perception of the type of treatment received, discomfort intensity, location of sensation, and duration of effects.
The results demonstrated that there was no statistically significant difference between groups regarding the perception of the type of stimulation received. The percentage of participants who believed they had received real acupuncture ranged from 69.56% to 91.30% at the ST-25 point and from 69.56% to 86.95% at the BL-52 point, with no significant differences between methods. Discomfort intensity was low and similar across all groups (p = 0.768). The needling sensation was reported as localized at the application point by most participants in all groups, not diffuse.
Interestingly, the duration of sensation was significantly longer in the real acupuncture group at the BL-52 point compared to some placebo groups, with the authors noting that the needling sensation may be a determining factor in whether the volunteer believes in the veracity of the technique. The mixed groups, which combined real acupuncture on one side of the body with placebo on the other, also presented results similar to the other groups. The clinical implications of this study are important for acupuncture research methodology. The results indicate that any of the three placebo methods tested can be used in future clinical trials, since all demonstrated similar efficacy in blinding participants.
This provides researchers with greater flexibility in choosing the most appropriate placebo method for their specific experimental design. The study contributes significantly to resolving controversies over which placebo method is most appropriate, a fundamental issue that has impacted the quality and interpretation of acupuncture studies. The absence of differences in perception between real and placebo acupuncture also raises interesting questions about the mechanisms by which acupuncture produces its therapeutic effects, highlighting the importance of nonspecific treatment components.
Strengths
- Large sample of 321 healthy participants
- Well-structured double-blind design
- Comparison of multiple validated placebo methods
- Rigorous standardization of procedures
- Use of acupuncture points in distinct anatomical regions
Limitations
- Study conducted only in healthy volunteers
- Did not evaluate therapeutic efficacy, only blinding
- Participants without prior acupuncture experience
- Single 30-minute session may not reflect real treatment

Expert Commentary
Clinical Relevance
For those conducting or evaluating acupuncture research, the choice of an appropriate placebo control is one of the most consequential — and most contested — methodological decisions. This randomized trial with 321 volunteers answers this question directly: the Park Sham device, the adhesive foam needle technique, and insertion with immediate removal produced rates of perceived real acupuncture indistinguishable from each other, ranging from 69.56% to 91.30% at the ST-25 point and from 69.56% to 86.95% at the BL-52 point, with no statistically significant difference between groups. In practice, this frees researchers to select the most logistically feasible control for each protocol without compromising blinding validity. In pain services that develop their own research programs, this operational flexibility has real impact on trial planning. The finding also reinforces that previous studies comparing acupuncture to any of these three placebos can be cross-referenced with greater methodological confidence.
Notable Findings
The finding that deserves the most attention is not the equivalence in blinding — expected by those who follow the literature — but the dissociation observed in the duration of sensation at the BL-52 point: this parameter was significantly longer in the real acupuncture group compared to some placebo groups. The authors note that the needling sensation, longer in the groups using invasive procedures, may be a determining factor in whether the volunteer believes in the veracity of the technique. The fact that the sensation was predominantly localized — not diffuse — in all groups is also worth noting.
From My Experience
In my practice at the Pain and Rehabilitation Center, the discussion of placebo in acupuncture often arises not only in the research context but also in conversations with skeptical patients who question whether the effect is 'real.' This study gives me an additional argument: even healthy volunteers, without any prior experience, cannot distinguish real from placebo acupuncture in a single session — which reinforces that the specificity of the stimulus goes far beyond simple skin contact. Over my career, I have observed that patients with chronic low back pain, for example, generally perceive a functional response after three to four sessions, and most reach a plateau of improvement between eight and twelve sessions. I routinely combine acupuncture with supervised therapeutic exercise and, when indicated, with pharmacological modulation. The profile that responds best, in my experience, is the patient with a predominant myofascial component, without established central sensitization — precisely where point specificity and insertion depth make a real clinical difference.
Dr. Marcus Yu Bin Pai · MD, PhD · Pain Medicine · Physical Medicine and Rehabilitation · Medical Acupuncture
PhD in Health Sciences, University of São Paulo. Board-certified in Pain Medicine, Physical Medicine and Rehabilitation, and Medical Acupuncture.
- 1AbdomenST 25
- 1BackBL 52
See the numbers: Where the cited points are
| Region | Points | Codes |
|---|---|---|
| Abdomen | 1 | ST 25 |
| Back | 1 | BL 52 |
Points cited
Full original article
Read the full scientific study
BMC Complementary and Alternative Medicine · 2016
DOI: 10.1186/s12906-016-1477-2
Scientific review
 Dr. Marcus Yu Bin Pai
Scientific lead · CRM-SP 158074 · RQE 65523 · 65524 · 655241
Medical disclaimer: This content is for educational purposes only and does not replace consultation, diagnosis, or treatment by a qualified professional. Some information may be assisted by artificial intelligence and is subject to inaccuracies. Always consult a physician.
Content reviewed by the medical team at CEIMEC — Integrated Centre for Chinese Medicine Studies, a reference in Medical Acupuncture for over 30 years.
- Strong
- Moderate
- Limited
- Weak
See the numbers: This study among the Library’s studies
| Study design | Clinical Trial Methodology | All studies |
|---|---|---|
| Meta-analysis · Systematic Review | 38 | 387 |
| RCT | 46 | 224 |
| Clinical Guideline | 2 | 5 |
| Observational | 5 | 38 |
| Case Series | 0 | 7 |
| Narrative Review | 10 | 155 |
| Preclinical / Animal | 0 | 6 |
| Other | 56 | 203 |
Related articles
Based on this article’s categories
Duan et al. · BMJ Evidence-Based Medicine · 2026
- Clinical Trial Methodology
- Safety & Adverse Events
- Systematic Reviews & Meta-Analyses
MacPherson et al. · Quality and Safety in Health Care · 2004
- Safety & Adverse Events
- Clinical Trial Methodology
Zhao et al. · Trials · 2011
- Safety & Adverse Events
- Clinical Trial Methodology
Boyce et al. · The International Journal of Sports Physical Therapy · 2020
- Dry Needling vs. Acupuncture
- Safety & Adverse Events
- Clinical Trial Methodology