Why Studying Acupuncture Is Hard
Acupuncture is often criticized for a supposed lack of "quality studies." The reality is more nuanced: there are more than 30,000 studies indexed in PubMed on acupuncture, including randomized clinical trials (RCTs), systematic reviews, and Cochrane meta-analyses. The problem is not the lack of research — it is that the methodological tools developed to evaluate medications encounter structural limitations when applied to an intervention like acupuncture.
Understanding these limitations isn't a defense of acupuncture — it's a requirement of scientific rigor. Evaluating any therapy fairly means understanding what studies can and cannot measure, and why.
This article examines the main methodological challenges in acupuncture research, what the available evidence actually shows, and how physicians and patients should interpret these data when making clinical decisions.
Double-Blind Impossible
In a drug trial, neither the patient nor the physician knows who is getting the active compound. In acupuncture, the practitioner always knows what they're doing — the double-blind is structurally unworkable.
Active Placebo
The "sham acupuncture" used as a control — needles in the wrong points or retractable needles — still activates Adelta and C nerve fibers, producing real physiological effects. The control group is not inert.
Individual Variability
Unlike a drug with a fixed dose, acupuncture is tailored to the patient — points, depth, frequency, and style vary. This individualization makes it hard to standardize protocols for RCTs.
Chronic Underfunding
Pharmaceutical research has billion-dollar commercial incentives. Acupuncture research is structurally underfunded — smaller studies, fewer participants, and shorter follow-up.
The Placebo Problem
The paradigm of the double-blind placebo-controlled clinical trial is the gold standard for medications. To apply it to acupuncture, researchers developed models of "sham acupuncture": Streitberger needles (retractable, that do not penetrate the skin), superficial needling at points outside the standardized therapeutic locations, and simulation with a deactivated laser.
These controls created a fundamental methodological paradox: sham acupuncture is not inert. Retractable needles still touch the skin and activate mechanoreceptors. Superficial needling outside classical points still stimulates Adelta and C nerve fibers, which are precisely the fibers associated with analgesic effects mediated by the endogenous opioid system.
The result is a triad of consistent findings in the literature:
Real acupuncture vs. No treatment
Real acupuncture consistently beats no treatment. The difference is statistically significant and clinically relevant for chronic pain, headache, and nausea.
Sham acupuncture vs. No treatment
Sham acupuncture also beats no treatment — confirming the control isn't inert and produces real physiological effects through neural mechanisms.
Real acupuncture vs. Sham acupuncture
The difference between real and sham is smaller, varying by condition. This does NOT mean acupuncture is just placebo — it may mean the sham is also an active intervention.
The clinically relevant question isn't whether acupuncture beats sham — it's whether acupuncture helps patients more than no treatment. And for several conditions, the answer is yes.
Evidence-based medicine perspective applied to acupuncture
The Context Effect: Placebo as a Real Mechanism
The work of neuroscientist Fabrizio Benedetti on the neurobiology of placebo demonstrated that placebo responses involve concrete physiological mechanisms: release of endogenous opioids, dopaminergic modulation, immune system activation, and measurable changes in biomarkers. Placebo is not "imagination" — it is a real neurobiological phenomenon.
Acupuncture has an exceptional capacity to amplify the therapeutic context effect: individualized physician attention, physical touch, structured ritual, positive expectation, and therapeutic environment. These components are legitimate treatment mechanisms — not "contaminants" to be eliminated.
Open-label placebo studies (open-label placebo) demonstrated efficacy even when the patient knows they are receiving placebo — reinforcing that the therapeutic context is a real and measurable intervention, not a deception.

Hierarchy and Types of Evidence
Evidence-based medicine organizes studies into a hierarchy that, in theory, runs from most to least reliable: systematic reviews and meta-analyses at the top, followed by RCTs, cohort studies, case series, and expert opinion. For acupuncture, though, this hierarchy needs to be read with caution.
The double-blind RCT — the gold standard for medications — has structural limitations for non-pharmacological interventions such as acupuncture, surgery, physical therapy, and psychotherapy. The British Medical Journal documented that a large share of established surgical interventions and medical procedures have never been evaluated by double-blind RCTs — and remain in the therapeutic arsenal based on other types of evidence.
Study Types and Their Limitations for Acupuncture
| Study Type | Strengths | Specific Limitations for Acupuncture |
|---|---|---|
| Double-blind RCT | Controls selection bias and expectation | Practitioner blinding impossible; sham control isn't inert; standardized protocols don't reflect real practice |
| Systematic review / Cochrane meta-analysis | Synthesizes evidence from multiple studies | Protocol heterogeneity hinders pooling; "garbage in, garbage out" |
| Pragmatic trial | Reflects real practice; compares acupuncture vs. conventional treatment | Doesn't control for expectation; weaker methodological control |
| Cohort and registry studies | Large samples; long follow-up; real-world outcomes | No randomization; uncontrolled confounders |
| Mechanistic studies (fMRI, biomarkers) | Measure objective physiological effects; don't rely on self-report | Do not directly demonstrate clinical efficacy; high cost |
Cochrane Reviews on Acupuncture
The Cochrane Collaboration — the global reference in evidence synthesis — has published systematic reviews on acupuncture for several conditions. Results vary in strength but are consistently more positive than the popular narrative suggests:
Cochrane Reviews on Acupuncture — Main Findings
Tension-type headache (prophylaxis)
Acupuncture reduces attack frequency comparably to pharmacological prophylaxis. Moderate to low quality evidence.
Migraine (prophylaxis)
Acupuncture shows efficacy comparable to preventive pharmacological treatment for reducing attack frequency; the effect over sham is small. Moderate-quality evidence.
Postoperative nausea and vomiting
Pericardium 6 (P6) significantly reduces nausea — one of the most robust findings in the acupuncture literature.
Chemotherapy-induced nausea and vomiting (CINV)
P6 stimulation reduces acute nausea. Moderate quality evidence; endorsed by ASCO and NCCN.
Chronic low back pain
Acupuncture beats passive controls (waiting list, usual care) for pain and function. Moderate quality evidence.
Knee osteoarthritis
Clinically relevant improvement in pain and function compared with controls. Moderate quality evidence.
Chronic neck pain
Evidence of short- and medium-term benefit for pain and disability. Moderate quality.
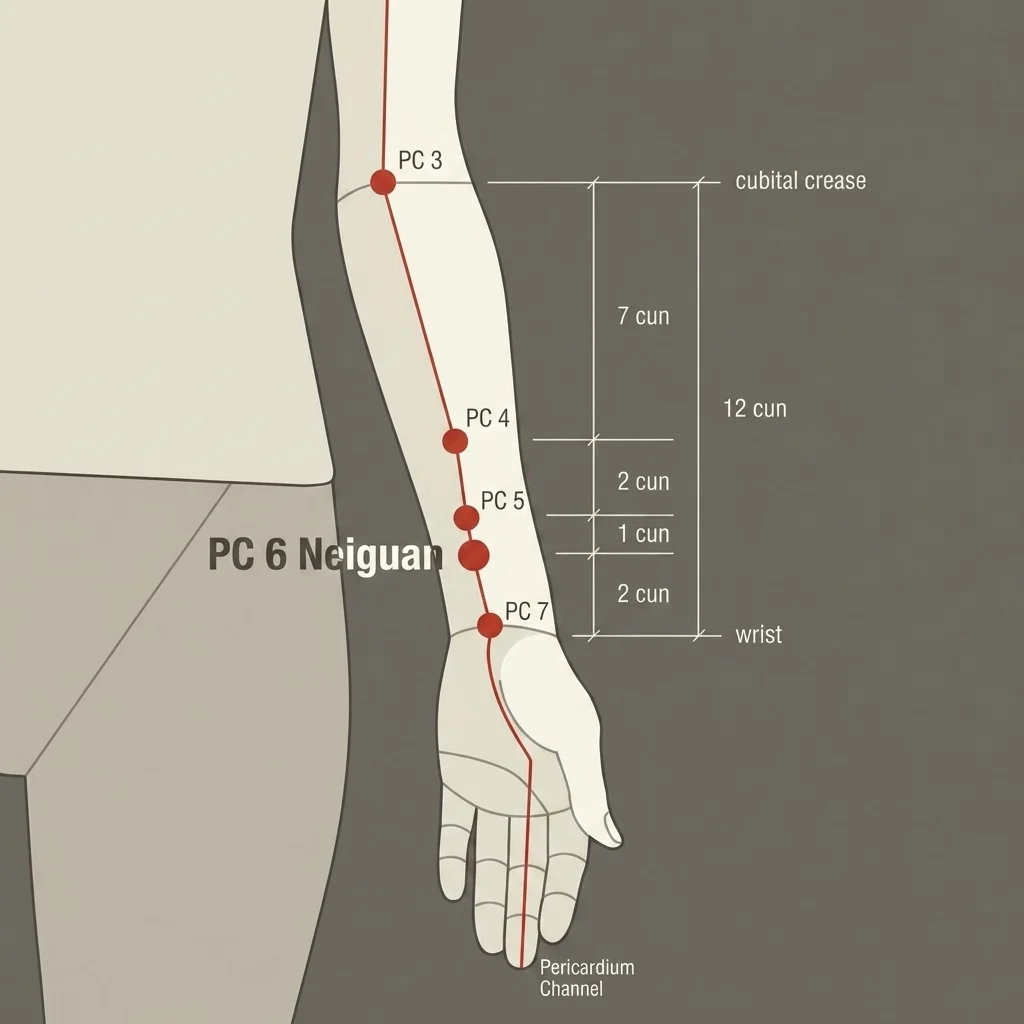
- Location
- On the palmar aspect of the forearm, 2 cun proximal to the transverse crease of the wrist, between the tendons of the palmaris longus and flexor carpi radialis muscles.
What the Studies Actually Show
Beyond Cochrane reviews, recognition of acupuncture by leading medical organizations reflects how the available evidence has been synthesized. These endorsements rest on formal reviews of the literature, not on tradition or belief.
Recognition by International Medical Organizations
Grade A — Strong Evidence
Tension-type headache and migraine (prophylaxis), postoperative nausea, chemotherapy-induced nausea and vomiting. High-quality Cochrane reviews.
Grade B — Moderate Evidence
Chronic low back pain, knee osteoarthritis, chronic neck pain, generalized chronic musculoskeletal pain. Multiple RCTs with consistent results.
Grade C — Emerging Evidence
Fibromyalgia, irritable bowel syndrome, dysmenorrhea, insomnia, cancer-related fatigue, CIPN. Positive studies, but with significant methodological limitations.
Limitations of the Existing Studies
Recognizing the positive evidence doesn't mean ignoring the real methodological limitations. An honest look at the acupuncture literature reveals structural problems that limit how certain we can be about the conclusions:
Main Methodological Limitations in Acupuncture Studies
- Small samples: most RCTs have fewer than 100 participants per group — too few to detect moderate effects with adequate statistical power
- Short follow-up: most studies end at 3 months; chronic pain is a long-term condition, só benefits and duration of effect are underestimated
- Heterogeneous protocols: traditional acupuncture, Western medical acupuncture, electroacupuncture, and auriculotherapy have distinct foundations — pooling them in meta-analyses dilutes the effects
- Publication bias: positive results are published more; neutral or negative results are underrepresented in the literature
- Variable methodological quality: much of the literature comes from Chinese journals with less stringent replication and peer review
- Lack of head-to-head studies: few directly compare acupuncture with standard pharmacotherapy, which limits conclusions about relative efficacy
- Lack of biomarker studies: few measure objective outcomes (inflammatory biomarkers, neuroimaging) beyond pain self-report
Current Scientific Consensus
The contemporary scientific position on acupuncture can be stated precisely: it isn't pseudoscience, it isn't magic, and it isn't a panacea. It's an intervention with plausible physiological mechanisms, positive evidence for specific conditions, and real methodological limitations that make definitive conclusions hard to draw.
The premise that "absence of evidence is evidence of absence" is a basic logical error. Absence of high-quality studies means the question has not yet been adequately investigated — not that the answer is negative. Evidence-based medicine consistently distinguishes between these two epistemic states.
The right question is not 'does acupuncture beat sham in RCTs?' — it is 'does acupuncture help patients more than no treatment?' For several well-studied conditions, the answer is yes, with evidence of sufficient quality to support clinical decisions.
How the evidence-based medicine perspective applies to non-pharmacological interventions
Why Acupuncture Is Not Pseudoscience
Pseudoscience ignores or rejects contrary evidence, resists falsification, and doesn't evolve with new knowledge. Modern medical acupuncture doesn't fit that definition:
Features That Distinguish Medical Acupuncture from Pseudoscience
Identified physiological mechanisms
Activation of Adelta and C fibers, modulation of the endogenous opioid system, effects on neurotransmitters and inflammatory cytokines — measurable by neuroimaging and biomarkers.
Animal model studies with reproducible results
Analgesic effects shown in animals rule out the placebo effect as the sole explanation.
Growing peer-reviewed literature of variable quality
Like any emerging scientific field: studies of uneven quality, with active debate and ongoing replication.
Evidence-based delimitation of indications
Medical acupuncture recognizes conditions with strong evidence (headache, nausea) and conditions with insufficient evidence — it doesn't claim to treat everything.
Recognition by rigorous regulatory bodies
ACP, ASCO, NCCN, NHS, WHO — organizations that reject homeopathy and other pseudosciences recognize acupuncture for specific indications.

Myths and Facts about Acupuncture Research
Myth vs. Fact
There are no studies on acupuncture
PubMed indexes more than 30,000 studies, including hundreds of RCTs and dozens of Cochrane reviews. The problem is quality and interpretation — not a shortage of research.
Acupuncture is just placebo effect
Animal studies demonstrate analgesia from acupuncture — excluding placebo as the sole explanation. In addition, the "context effect" (neurobiological placebo) is a real physiological mechanism, not an illusion, and acupuncture amplifies it legitimately.
If it were real, there would be a perfect RCT proving it
Many accepted medical interventions, such as various surgeries and procedures, have never been evaluated in double-blind RCTs. The standard of proof varies with the nature of the intervention. For acupuncture, the double-blind is structurally impossible.
Any observed effect can be explained by therapist attention
Functional neuroimaging (fMRI) shows that acupuncture produces specific changes in pain-related brain regions, distinct from those seen with control stimuli. Animal studies using automated electronic acupuncture replicate analgesic effects without any human interaction.
Similar effects from sham and real acupuncture prove that acupuncture doesn't work
This reasoning assumes sham is inert — a premise that's been refuted. If sham also produces real neural effects, comparing real with sham measures the difference between two active treatments, not between treatment and placebo.
How the Patient Should Interpret the Evidence
For a patient weighing acupuncture as a therapeutic option, the practical question is: how do you make sense of a field with positive but methodologically imperfect evidence?
The answer rests on a few principles of shared decision-making that any serious medical acupuncturist should apply:
- For conditions with favorable evidence (stronger for headache and nausea; moderate for chronic low back pain and knee osteoarthritis), acupuncture is a legitimate option.
- For severe conditions, or those with conventional treatments of high proven efficacy, acupuncture is best positioned as a complementary therapy, not a substitute.
- The practitioner's quality matters.
Frequently Asked Questions
Frequently Asked Questions
PubMed indexes more than 30,000 studies on acupuncture, including hundreds of randomized clinical trials and dozens of Cochrane systematic reviews. The field has grown significantly over the past two decades, with a marked increase in high-quality studies. The challenge isn't a lack of research — it's methodological heterogeneity and the difficulty of applying the double-blind paradigm to an intervention like acupuncture.
In a double-blind pharmacological trial, neither the patient nor the physician knows who is receiving the active medication or the placebo. In acupuncture, the practitioner always knows exactly what they are doing — it is not possible to mask the procedure from the person performing it. This is the só-called "impossible blind problem." The patient can be partially blinded with sham acupuncture, but the practitioner never can. This creates a form of potential bias that does not exist in pharmacological trials.
Sham acupuncture is the control used in clinical studies to mimic real acupuncture without — in theory — its active effects. Models include Streitberger needles (retractable, non-penetrating), superficial needling at locations outside classical points, and simulation with a deactivated laser. The problem is that none of these controls are truly inert: retractable needles stimulate cutaneous mechanoreceptors, and superficial needling activates Adelta and C nerve fibers. Studies consistently show that sham also outperforms no treatment, confirming that the control has real physiological effects.
Yes. The American College of Physicians (ACP) lists acupuncture among the first-line non-pharmacological therapies for acute and chronic low back pain. The American Society of Clinical Oncology (ASCO) and the National Comprehensive Cancer Network (NCCN) recognize acupuncture for chemotherapy-induced peripheral neuropathy and for managing oncology symptoms. The British NHS and the NICE guidelines recognize acupuncture for chronic tension-type headache and migraine. The World Health Organization, in a 2003 report (since superseded by more recent reviews), listed 64 conditions with preliminary evidence of benefit.
No — and this is one of the most common misconceptions about acupuncture research. First, the placebo effect is a real neurobiological phenomenon: it involves release of endogenous opioids, dopaminergic modulation, and measurable changes in biomarkers. Second, sham acupuncture — the "placebo" used in studies — has been shown to be itself physiologically active, making the real vs. sham comparison a comparison between two active treatments. Third, real acupuncture is consistently superior to no treatment, which is the clinically relevant comparison for the patient.
The conditions with the most robust evidence (moderate- to high-quality Cochrane reviews) are migraine prophylaxis, chronic tension-type headache prophylaxis, postoperative nausea and vomiting (point P6), and chemotherapy-induced nausea. With moderate evidence: chronic low back pain, knee osteoarthritis, and chronic neck pain. With emerging but less conclusive evidence: fibromyalgia, irritable bowel syndrome, dysmenorrhea, insomnia, and cancer-related fatigue.
Several factors explain why results vary: (1) different protocols — studies use different points, techniques, frequencies, and durations; (2) different conditions — results for low back pain don't generalize to other conditions; (3) variable methodological quality — small-sample studies produce more unstable results; (4) practitioners with different training; (5) patient populations that differ in severity, chronicity, and comorbidities. A meta-analysis that pools methodologically heterogeneous studies can yield less reliable conclusions than well-conducted individual trials.
Yes, in relevant respects. Medical acupuncture (practiced by physicians trained in Western medicine) uses acupuncture points and techniques within a modern diagnostic and clinical framework, selecting points based on neuroanatomical and physiological evidence. This differs from traditional acupuncture, which rests exclusively on pré-scientific concepts of point classification and energy flow. Studies of evidence-based standardized protocols apply more directly to medical acupuncture practice than studies using protocols built around traditional Chinese diagnoses.
The most relevant limitations are: (1) small samples — most RCTs enroll fewer than 100 participants per group, which reduces statistical power; (2) short follow-up — most end at 3 months, while chronic pain requires long-term assessment; (3) protocol heterogeneity — making direct comparison between studies impossible; (4) publication bias — positive results get published more often; (5) the impossibility of perfect double-blinding; (6) sham controls with their own physiological activity; (7) variable study quality, especially in trials published in Chinese journals.
Patients should consider: (1) whether their condition has evidence of benefit with acupuncture — for conditions with favorable evidence (headache and nausea; low back pain, with moderate evidence), acupuncture is a legitimate option; (2) whether there are reasons to prefer or complement it with acupuncture — medication intolerance, preference for a lower pharmacological burden, interest in an integrative approach; (3) whether the practitioner is a physician with recognized training; (4) whether acupuncture is proposed as a complement to conventional treatment, not as a substitute; (5) realistic expectations — acupuncture isn't a universal cure, but it can be a valuable therapeutic tool when properly indicated and practiced by a qualified physician.
Related Reading
Deepen your knowledge with related articles