Electroacupuncture
Main result
34.5%
Reduction in infarct volume
PLoS ONE · Kim et al. · 2013
Electroacupuncture Acutely Improves Cerebral Blood Flow and Attenuates Moderate Ischemic Injury via an Endothelial Mechanism in Mice
Weak
Limited
Moderate
Strong
12.4 %
Increase in cerebral blood flow
p < 0.05
Improvement in neurologic function
Study design sheet
- Controlled Experimental Study
- n=4–10 mice per group
- High Scientific Impact
- Duration
24 hours of follow-up
20 minutes of electroacupuncture, assessment after 24 hours
- OBJECTIVE
- To investigate whether electroacupuncture applied immediately after cerebral ischemia improves blood flow and reduces neurologic damage
- WHO
- Male mice with experimentally induced cerebral ischemia
- POINTS
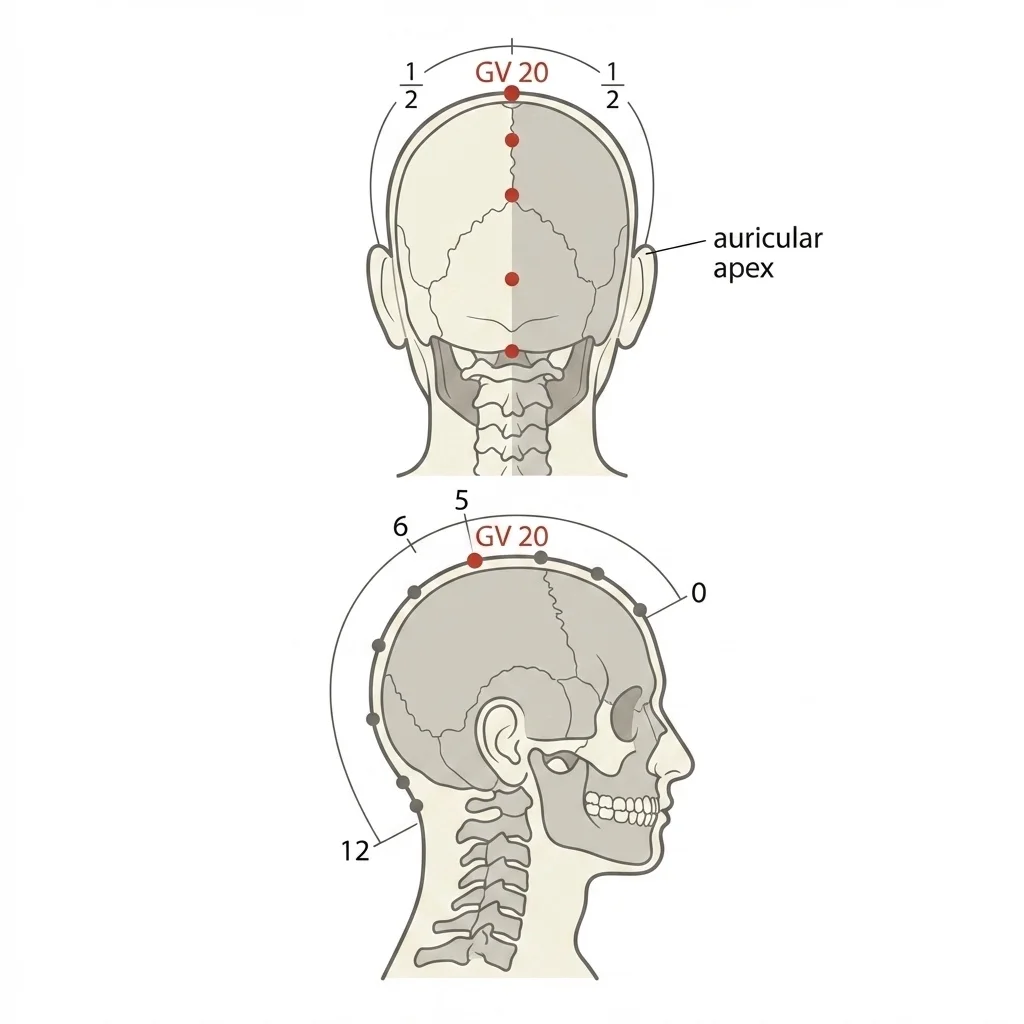
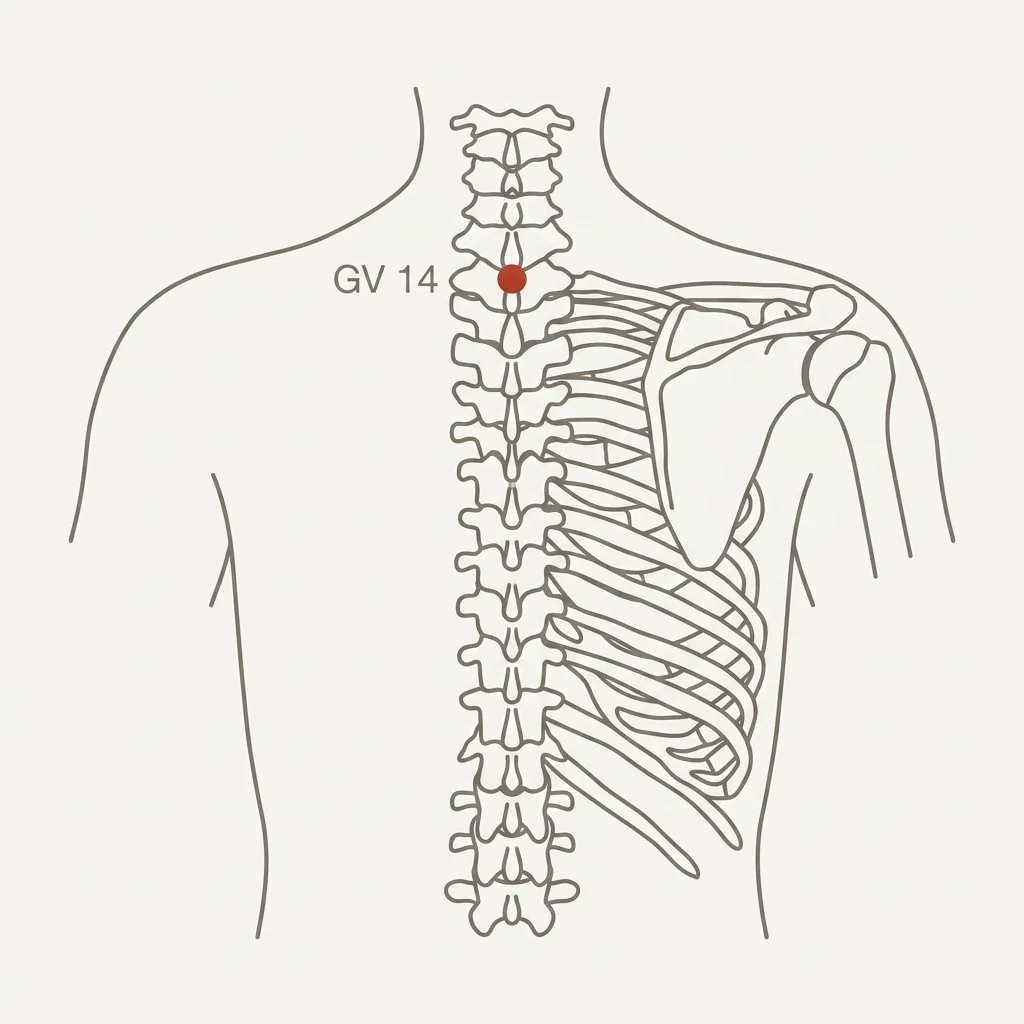
- Baihui (GV-20) and Dazhui (GV-14), stimulated at 1 mA and 2 Hz
- Results in numbers
- 34.5 %Reduction in infarct volume
- 12.4 %Increase in cerebral blood flow
- p < 0.05Improvement in neurologic function
- 1.57 vs 0.33 pmol/LIncrease in cortical acetylcholine
What does this mean for you?
This study shows that electroacupuncture applied shortly after a stroke can improve blood flow to the brain and significantly reduce brain damage. The treatment was most effective in moderate stroke cases, working by increasing the production of nitric oxide, which dilates blood vessels.
Article summary
Plain-language narrative summary
Electroacupuncture is a promising therapeutic approach that combines traditional needling with modern electrotherapy for the treatment of various neurologic conditions, including ischemic stroke. This health problem remains one of the leading causes of death and disability worldwide, with few truly effective treatment options in the acute phase. Although prior research has demonstrated benefits of electroacupuncture in preventive treatments or rehabilitation after stroke, its immediate application during the acute phase of the ischemic event still required better scientific understanding of the mechanisms involved and its actual efficacy.
This experimental study, conducted by South Korean researchers in mice, aimed primarily to investigate whether electroacupuncture applied immediately after a cerebral ischemic event could improve both tissue damage and functional recovery in the animals. The researchers used two specific acupoints: Baihui (GV-20), located at the top of the head, and Dazhui (GV-14), located in the posterior cervical region. These points were chosen because they are traditionally associated with the treatment of brain and spinal cord disorders in Korean medicine. To test their hypothesis, the researchers artificially induced moderate and severe cerebral strokes in mice by temporarily blocking the middle cerebral artery for 60 or 90 minutes, respectively.
Electroacupuncture treatment was applied immediately after the onset of vascular occlusion, using low-intensity electrical stimuli for 20 minutes.
The results demonstrated that electroacupuncture was able to significantly increase cerebral blood flow, improving perfusion in the cortical region of the brain by approximately 12% relative to baseline levels. This beneficial effect lasted for approximately 20 minutes after the end of treatment. Importantly, this improvement in cerebral circulation was not accompanied by changes in systemic blood pressure, suggesting a local and brain-specific effect. Through experiments with different pharmacologic blockers, the researchers identified that the mechanism responsible for this benefit involves the release of acetylcholine, a neurotransmitter that acts on specific muscarinic receptors in cerebral blood vessels.
This cascade of events results in the production of nitric oxide by vascular endothelial cells, causing vasodilation and consequently increased blood flow. When they tested electroacupuncture in genetically modified mice lacking the enzyme responsible for endothelial nitric oxide production, the perfusion response elicited by electroacupuncture was significantly attenuated and the effect on moderate ischemic injury was totally abolished, which, according to the authors, suggests the importance of this molecular pathway.
For patients and healthcare professionals, these findings have important and encouraging clinical implications. Electroacupuncture proved effective specifically in moderate-intensity strokes, reducing the size of the injured brain area by an impressive 34.5% compared to the control group. This reduction in tissue damage translated into significant functional improvements, with treated animals showing better neurologic and motor performance on assessments performed 24 hours after the stroke. These results suggest that electroacupuncture may be a valuable therapeutic tool when applied early in cases of moderate stroke, potentially reducing sequelae and accelerating recovery.
The article mentions, as background, that electroacupuncture is economical, easily performed and has few adverse effects, but this mouse study did not assess cost or safety, and the authors stress that more evidence is needed before acute electroacupuncture is accepted clinically. The results provide a scientific basis for better understanding the cerebrovascular mechanisms involved.
However, it is essential to recognize the limitations of this study for an appropriate interpretation of the results. First, the research was conducted exclusively in animal models, and we know that benefits observed in mice do not always translate directly to humans because of physiological differences between species. Second, electroacupuncture proved effective only in moderate-intensity strokes, showing no benefits in more severe cases, suggesting that there is a specific therapeutic window for its application. Third, the study evaluated only short-term effects; additional research is needed to understand long-term benefits.
In addition, it will be crucial to determine precisely the maximum time after stroke onset during which electroacupuncture can still be effective — essential information for its practical clinical application. Future studies in humans are needed to confirm these promising findings and establish safe and effective treatment protocols, taking into account the particularities of different types of stroke and patient populations.
Strengths
- Well-controlled methodology
- Detailed mechanistic investigation
- Use of appropriate control groups
- Multiple outcome measures
Limitations
- Animal study only
- Effectiveness limited to moderate stroke
- Therapeutic window not fully defined
- Requires clinical validation

Expert Commentary
Clinical Relevance
What this work brings to neurorehabilitation practice is the characterization of a plausible endothelial mechanism by which electroacupuncture at GV-20 and GV-14 increases cortical perfusion without altering systemic blood pressure — a hemodynamic safety finding relevant to the acute stroke setting, where pressure variations are undesirable. The 34.5% reduction in infarct volume in moderate ischemia and the 12.4% increase in cerebral blood flow support the hypothesis that early electroacupuncture may exert tissue protection in moderate-intensity ischemia. This mouse study did not test combination with thrombolysis or thrombectomy, nor specific patient populations, and the authors themselves state that more evidence is needed before acute treatment is accepted clinically. The acetylcholine–muscarinic receptor–eNOS–nitric oxide pathway identified in this model also connects electroacupuncture to mechanisms already recognized in cardiology and vascular neurology.
Notable Findings
The most noteworthy finding is not just the magnitude of infarct reduction, but the specificity of the molecular pathway demonstrated with the eNOS knockout model: without endothelium-derived nitric oxide, the perfusion response was significantly attenuated and the effect on moderate ischemic injury was totally abolished. This distinguishes electroacupuncture from interventions with nonspecific systemic action and positions the cerebral endothelium as a neurally mediated therapeutic target. The cortical acetylcholine differential — 1.57 versus 0.33 pmol/L between treated and control groups — suggests that electrical stimulation activates central cholinergic pathways with biologically significant intensity. Another point worth highlighting is the absence of benefit in severe ischemia, which indicates that, in this model, the benefit occurred after 60 minutes of occlusion (moderate ischemia) but not after 90 minutes (severe ischemia); the article does not explain this difference.
From My Experience
In my stroke rehabilitation practice, I have followed with growing interest the role of electroacupuncture in the subacute phase, and this study reinforces a hypothesis that circulates in the most experienced services: the timing of intervention is as critical as the technique itself. When we initiate electroacupuncture in the first days post-stroke — usually at GV-20 combined with motor points of the affected limb — I typically observe a perceptible functional response between the third and fifth session, with gains in tone, proximal motor control, and, eventually, spasticity. For neurologic rehabilitation after moderate stroke, the cycle we use in our service is approximately 12 to 20 sessions during the intensive phase, with subsequent monthly maintenance. We combine electroacupuncture with neurologic physical therapy and, when available, functional electrical stimulation — the synergy between these approaches surpasses each one alone. The profile that responds best, in my experience, is the patient with moderate-grade cortical stroke, without severe cognitive impairment that prevents cooperation, and with less than three weeks of evolution at the start of treatment.
Dr. Marcus Yu Bin Pai · MD, PhD · Pain Medicine · Physical Medicine and Rehabilitation · Medical Acupuncture
PhD in Health Sciences, University of São Paulo. Board-certified in Pain Medicine, Physical Medicine and Rehabilitation, and Medical Acupuncture.
- 1HeadGV 20
- 1NeckGV 14
See the numbers: Where the cited points are
| Region | Points | Codes |
|---|---|---|
| Head | 1 | GV 20 |
| Neck | 1 | GV 14 |
Points cited
Full original article
Read the full scientific study
PLoS ONE · 2013
DOI: 10.1371/journal.pone.0056736
Scientific review
 Dr. Marcus Yu Bin Pai
Scientific lead · CRM-SP 158074 · RQE 65523 · 65524 · 655241
Medical disclaimer: This content is for educational purposes only and does not replace consultation, diagnosis, or treatment by a qualified professional. Some information may be assisted by artificial intelligence and is subject to inaccuracies. Always consult a physician.
Content reviewed by the medical team at CEIMEC — Integrated Centre for Chinese Medicine Studies, a reference in Medical Acupuncture for over 30 years.
- Strong
- Moderate
- Limited
- Weak
See the numbers: This study among the Library’s studies
| Study design | Electroacupuncture | All studies |
|---|---|---|
| Meta-analysis · Systematic Review | 21 | 387 |
| RCT | 26 | 224 |
| Clinical Guideline | 1 | 5 |
| Observational | 0 | 38 |
| Case Series | 1 | 7 |
| Narrative Review | 8 | 155 |
| Preclinical / Animal | 4 | 6 |
| Other | 24 | 203 |
Related articles
Based on this article’s categories
Napadow et al. · Cerebral Cortex · 2014
- Mechanisms of Action
- Neurology & Stroke Rehab
- Electroacupuncture
Lin et al. · Molecular Medicine Reports · 2016
- Electroacupuncture
- Neurology & Stroke Rehab
- Mechanisms of Action
Maeda et al. · Brain · 2017
- Electroacupuncture
- Mechanisms of Action
Hui et al. · Autonomic Neuroscience · 2010
- Mechanisms of Action
- Chronic Pain
- Neurology & Stroke Rehab