Mechanisms of Action
Main result
−21.6points
Itch reduction (electroacupuncture)
Change within the treated group
Crossover RCT with neuroimaging · Cerebral Cortex · Napadow et al. · 2014 · 14 participants
The Brain Circuitry Mediating Antipruritic Effects of Acupuncture
Weak
Limited
Moderate
Strong
- Electroacupuncture14 participants
- Placebo acupuncture14 participants
Significant
Reduction in brain activation - insula
Significant
Reduction in brain activation - putamen
Study design sheet
- n=14 participants
- High impact - neuroimaging
- Design
- Crossover RCT with neuroimaging
- Participants
- 14
n = 14; median of studies with the same design: 79
- Duration
4 MRI sessions, separated by at least 1 week
4 neuroimaging sessions, separated by at least 1 week
- Groups
- Electroacupuncture (14)True points with 100 Hz electrostimulation
- Placebo acupuncture (14)Sham points without skin penetration
- Antihistamine (14)Oral levocetirizine 5 mg
- Drug placebo (14)Similar-tasting placebo solution
- OBJECTIVE
- To investigate the brain mechanisms by which acupuncture reduces itch in patients with atopic dermatitis
- WHO
- 14 patients with atopic dermatitis and confirmed allergic sensitivity
- POINTS
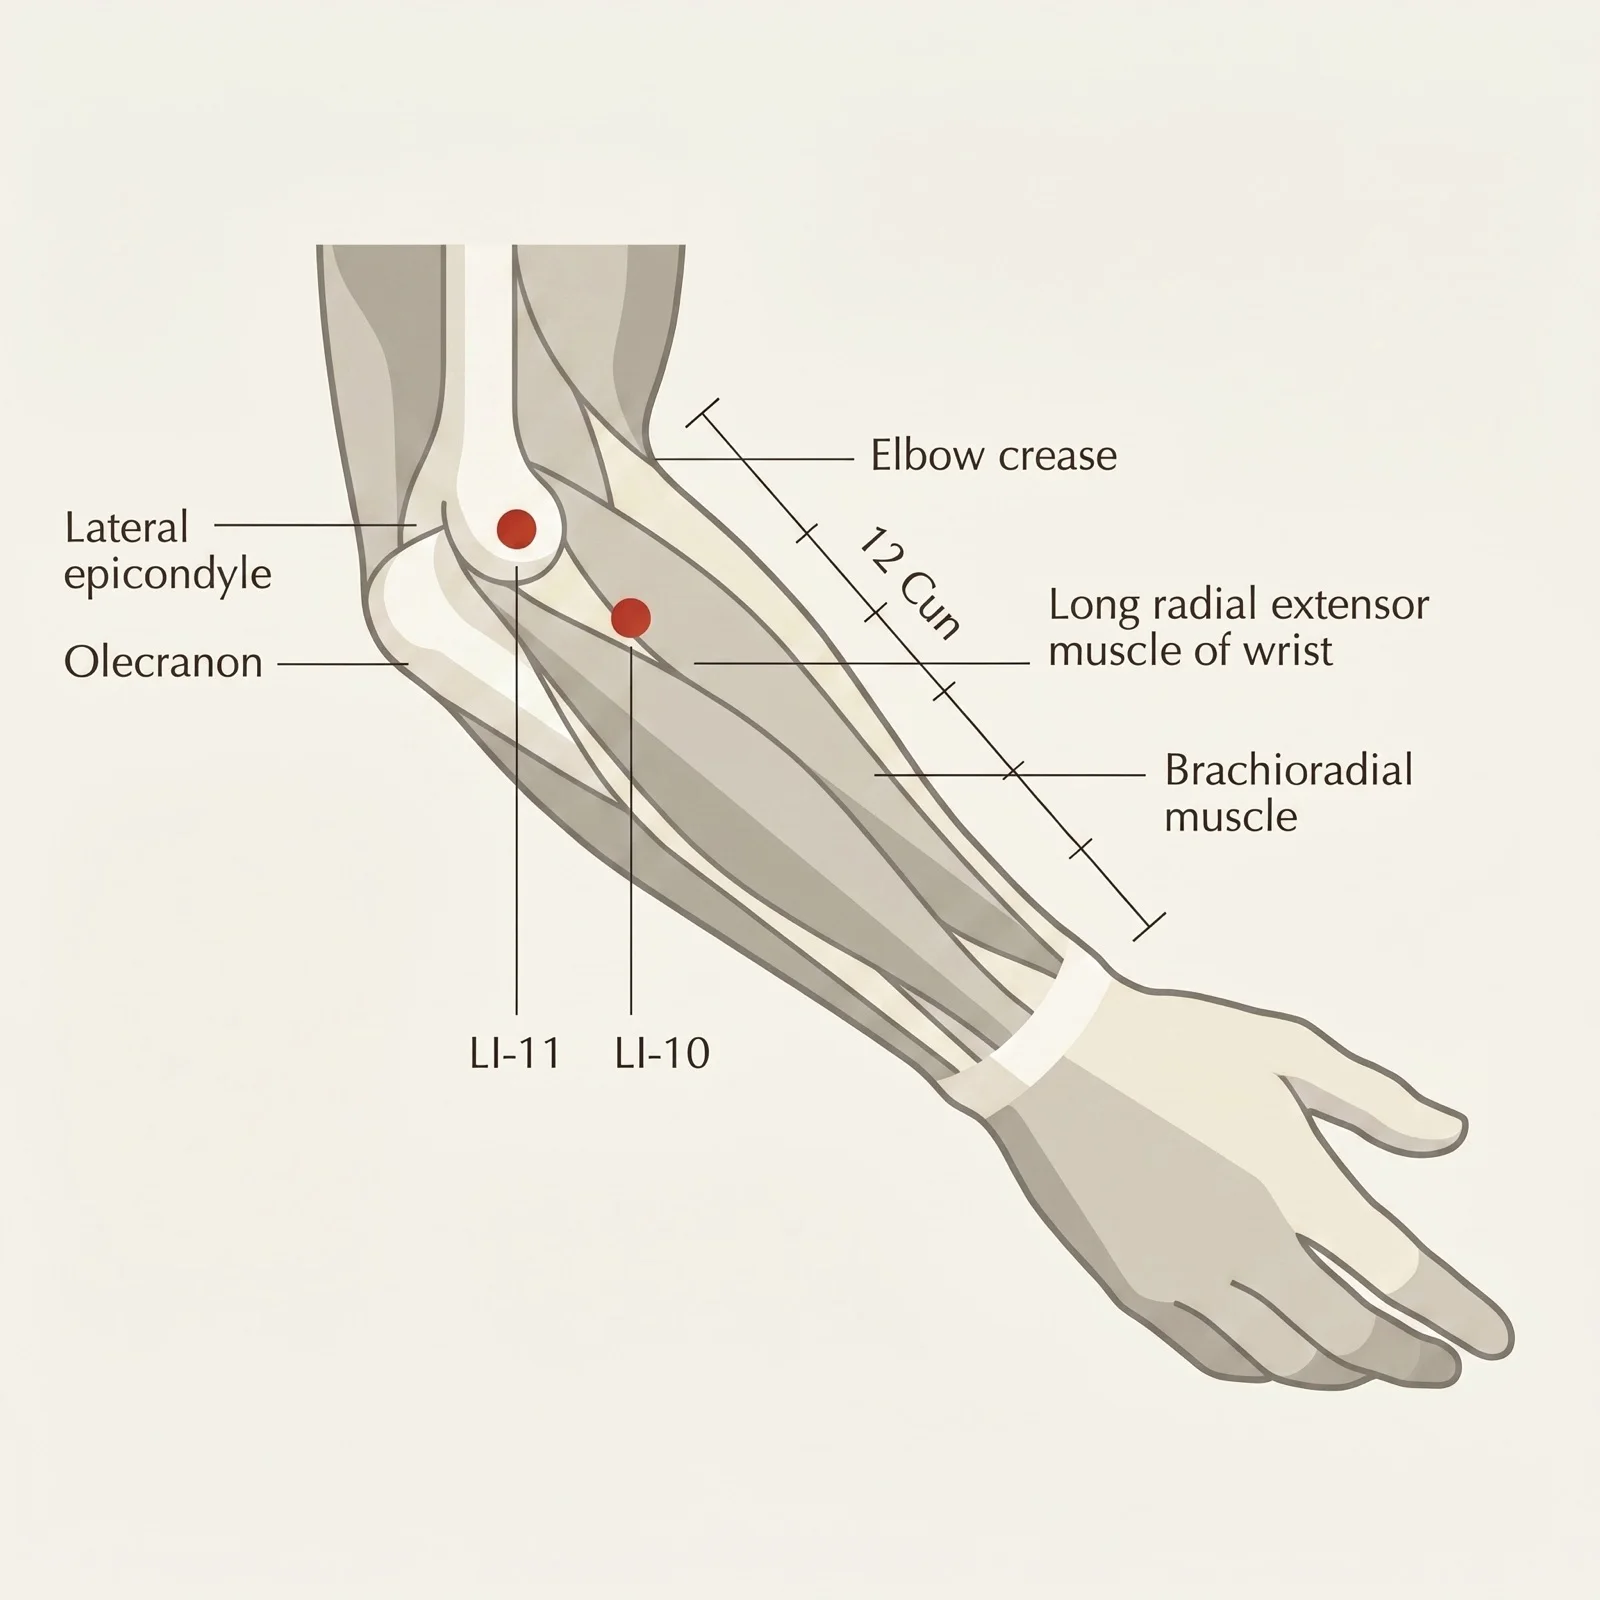
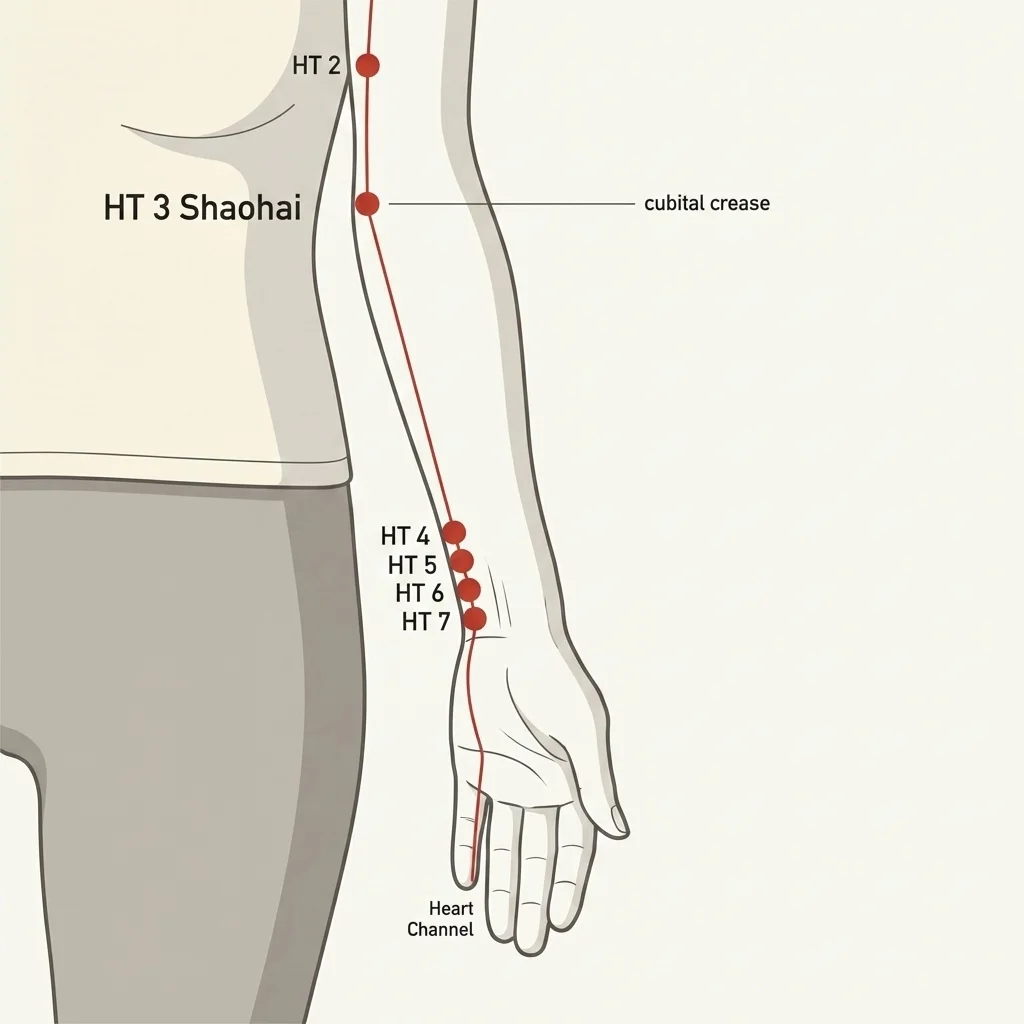
- LI-11 (Quchi) and HT-3 (Shaohai), near the right elbow
- Results in numbers
- −21.6 pointsItch reduction (electroacupuncture)
- SignificantReduction in brain activation - insula
- SignificantReduction in brain activation - putamen
- No differenceAntihistamine efficacy
What does this mean for you?
This study showed that acupuncture with electrical stimulation can significantly reduce itch in people with atopic dermatitis by altering activity in specific areas of the brain. The antihistamine, in turn, did not reduce itch in this model, which, according to the authors, suggests that histamine may not be an important mediator of itch in atopic dermatitis.
Article summary
Plain-language narrative summary
This innovative study used functional MRI to investigate how acupuncture reduces itch in patients with atopic dermatitis, a chronic condition that significantly affects quality of life. The researchers developed a sophisticated experimental model in which itch was induced through allergens applied to the skin, and its intensity was modulated by temperature changes, allowing detailed analysis of brain responses at different phases of the itch sensation. Fourteen patients with atopic dermatitis participated in a crossover study in which each experienced four different interventions: real electroacupuncture, placebo acupuncture (no skin penetration), oral antihistamine (levocetirizine), and drug placebo. Electroacupuncture was applied to specific points near the right elbow (LI-11 and HT-3) with 100 Hz electrical stimulation, following protocols validated in previous studies.
The sessions were separated by at least one week to avoid residual effects. The results revealed that itch perception involves different brain circuits depending on the phase of the sensation. During the initial rising phase of itch, areas related to salience and motivation were activated, including the anterior insula and the striatum (specifically the putamen). When itch reached its maximum peak, robust activation was observed in the dorsolateral prefrontal cortex and premotor areas, likely reflecting the cognitive control needed to suppress the urge to scratch.
Electroacupuncture demonstrated significant efficacy, reducing itch intensity by an average of 21.6 points on a 0-100 scale. This improvement was accompanied by a reduction in brain activation in several key regions: anterior insula, putamen, globus pallidus, and prefrontal cortex. Particularly important was the finding that the reduction in putamen activation correlated directly with the decrease in itch, suggesting that this brain region, involved in motivational processing and habitual behaviors, plays a central role in the antipruritic effects of acupuncture. Surprisingly, the antihistamine levocetirizine showed no efficacy in this experimental model, altering neither itch intensity nor brain activation.
This finding contrasts with previous studies and suggests that histamine may not be an important mediator of itch in atopic dermatitis, and that other, perhaps brain-derived attentional mechanisms may support the relief seen with antihistamines. Placebo acupuncture, associated with markedly less somatosensory afference, also did not reduce itch; according to the authors, the somatosensory aspect of the intervention may be important for its antipruritic effect. The study offers valuable insights into the neurobiological mechanisms of itch and its relief through acupuncture. The identification of the putamen as a key region suggests that acupuncture may function as a counterstimulus, modulating the brain circuits that process the urge to scratch.
This finding has important implications for the development of new therapies, especially considering that conventional treatments are often inadequate for chronic itch. Limitations include the relatively small sample size and the fact that the study evaluated only acute effects, not the benefits of a prolonged course of acupuncture treatment. In addition, the experimental model may not fully reflect the complexity of chronic itch in the real clinical setting. Despite these limitations, this work represents a significant advance in understanding the brain mechanisms underlying the therapeutic effects of acupuncture.
Strengths
- First study to use neuroimaging to investigate antipruritic mechanisms of acupuncture
- Robust crossover design with multiple controls
- Well-validated experimental model with temperature control
- Sophisticated analysis separating different phases of itch
Limitations
- Small sample (n=14)
- Evaluation of acute effects only, not chronic
- Partially blinded study (investigator was not blinded)
- Experimental model may not reflect real clinical itch
Expert Commentary
Clinical Relevance
Chronic pruritus in atopic dermatitis remains one of the most refractory symptoms in dermatologic and allergy practice, and this work by Napadow and colleagues offers a mechanistic contribution: in an experimental model of allergen-induced itch, electroacupuncture reduced itch and the activation of central brain circuits — specifically the anterior insula and the putamen — which did not occur with levocetirizine. The authors conclude that histamine may not be an important mediator of itch in atopic dermatitis. This was a study of 14 patients with a single session per intervention that evaluated only the acute antipruritic effect; it did not include antihistamine-refractory patients or assess a course of sessions, so the clinical application of these findings depends on further studies.
Notable Findings
The dissociation between phases of itch — rising versus maximum peak — revealing distinct brain circuits is a finding of rare neurobiological elegance in acupuncture studies. The rising phase recruits regions of salience and motivation, while the peak involves the dorsolateral prefrontal cortex in an apparent effort to suppress the urge to scratch. Electroacupuncture attenuated both components, with an average reduction of 21.6 points in itch intensity and simultaneous modulation of the insula, putamen, and globus pallidus. The direct correlation between reduced putamen activation and clinical relief is particularly intriguing, as it positions the striatum (putamen) — a central structure in habitual and motivational behaviors — as a functional target of the intervention. The absence of response to levocetirizine in this model, in turn, is consistent with the authors' conclusion that histamine may not be an important mediator of itch in atopic dermatitis.
From My Experience
At the Pain Center of HC-FMUSP, we have been treating patients with chronic pruritus associated with dermatologic and neuropathic conditions, and the pattern I have observed for decades is consistent with what this work demonstrates: response to electroacupuncture usually appears after the second or third session, with noticeable relief of nocturnal itch — which is what most compromises sleep and quality of life. In general, I work with cycles of eight to ten weekly sessions before evaluating maintenance, reducing to biweekly when there is a sustained response. I typically combine LI-11 with SP-10 in these cases, and the 100 Hz frequency as used in the study is the one I prefer for acute analgesic and antipruritic effects. Patients with intense dermographism or previous use of immunosuppressants respond more heterogeneously, requiring protocol adjustments. When itch has a strong anxious component or associated insomnia, the combination with points of the heart meridian potentiates the result in a way I have observed clinically for many years.
Prof. Dr. Hong Jin Pai · PhD in Sciences, University of São Paulo
Specialist physician in Medical Acupuncture. Adjunct Professor at the Institute of Orthopedics, HC-FMUSP. Coordinator of the Acupuncture Group at the HC-FMUSP Pain Center.
- 2Upper LimbLI 11 · HT 3
See the numbers: Where the cited points are
| Region | Points | Codes |
|---|---|---|
| Upper Limb | 2 | LI 11, HT 3 |
Points cited
Full original article
Read the full scientific study
Cerebral Cortex · 2014
DOI: 10.1093/cercor/bhs363
Scientific review
 Dr. Marcus Yu Bin Pai
Scientific lead · CRM-SP 158074 · RQE 65523 · 65524 · 655241
Medical disclaimer: This content is for educational purposes only and does not replace consultation, diagnosis, or treatment by a qualified professional. Some information may be assisted by artificial intelligence and is subject to inaccuracies. Always consult a physician.
Content reviewed by the medical team at CEIMEC — Integrated Centre for Chinese Medicine Studies, a reference in Medical Acupuncture for over 30 years.
- Strong
- Moderate
- Limited
- Weak
See the numbers: This study among the Library’s studies
| Study design | Mechanisms of Action | All studies |
|---|---|---|
| Meta-analysis · Systematic Review | 35 | 387 |
| RCT | 24 | 224 |
| Clinical Guideline | 0 | 5 |
| Observational | 8 | 38 |
| Case Series | 1 | 7 |
| Narrative Review | 79 | 155 |
| Preclinical / Animal | 4 | 6 |
| Other | 80 | 203 |
Related articles
Based on this article’s categories
Kim et al. · PLoS ONE · 2013
- Electroacupuncture
- Neurology & Stroke Rehab
- Mechanisms of Action
Lin et al. · Molecular Medicine Reports · 2016
- Electroacupuncture
- Neurology & Stroke Rehab
- Mechanisms of Action
Maeda et al. · Brain · 2017
- Electroacupuncture
- Mechanisms of Action
Hui et al. · Autonomic Neuroscience · 2010
- Mechanisms of Action
- Chronic Pain
- Neurology & Stroke Rehab